
A 62-year-old former smoker completes outpatient pulmonary function testing for progressive dyspnea. Results show reduced FEV1, reduced FEV1/FVC ratio, increased residual volume and total lung capacity, and reduced DLCO corrected for hemoglobin. Which PFT pattern interpretation best fits these spirometry, lung volume, and DLCO findings?
Select an answer to reveal the explanation.
Short Explanation
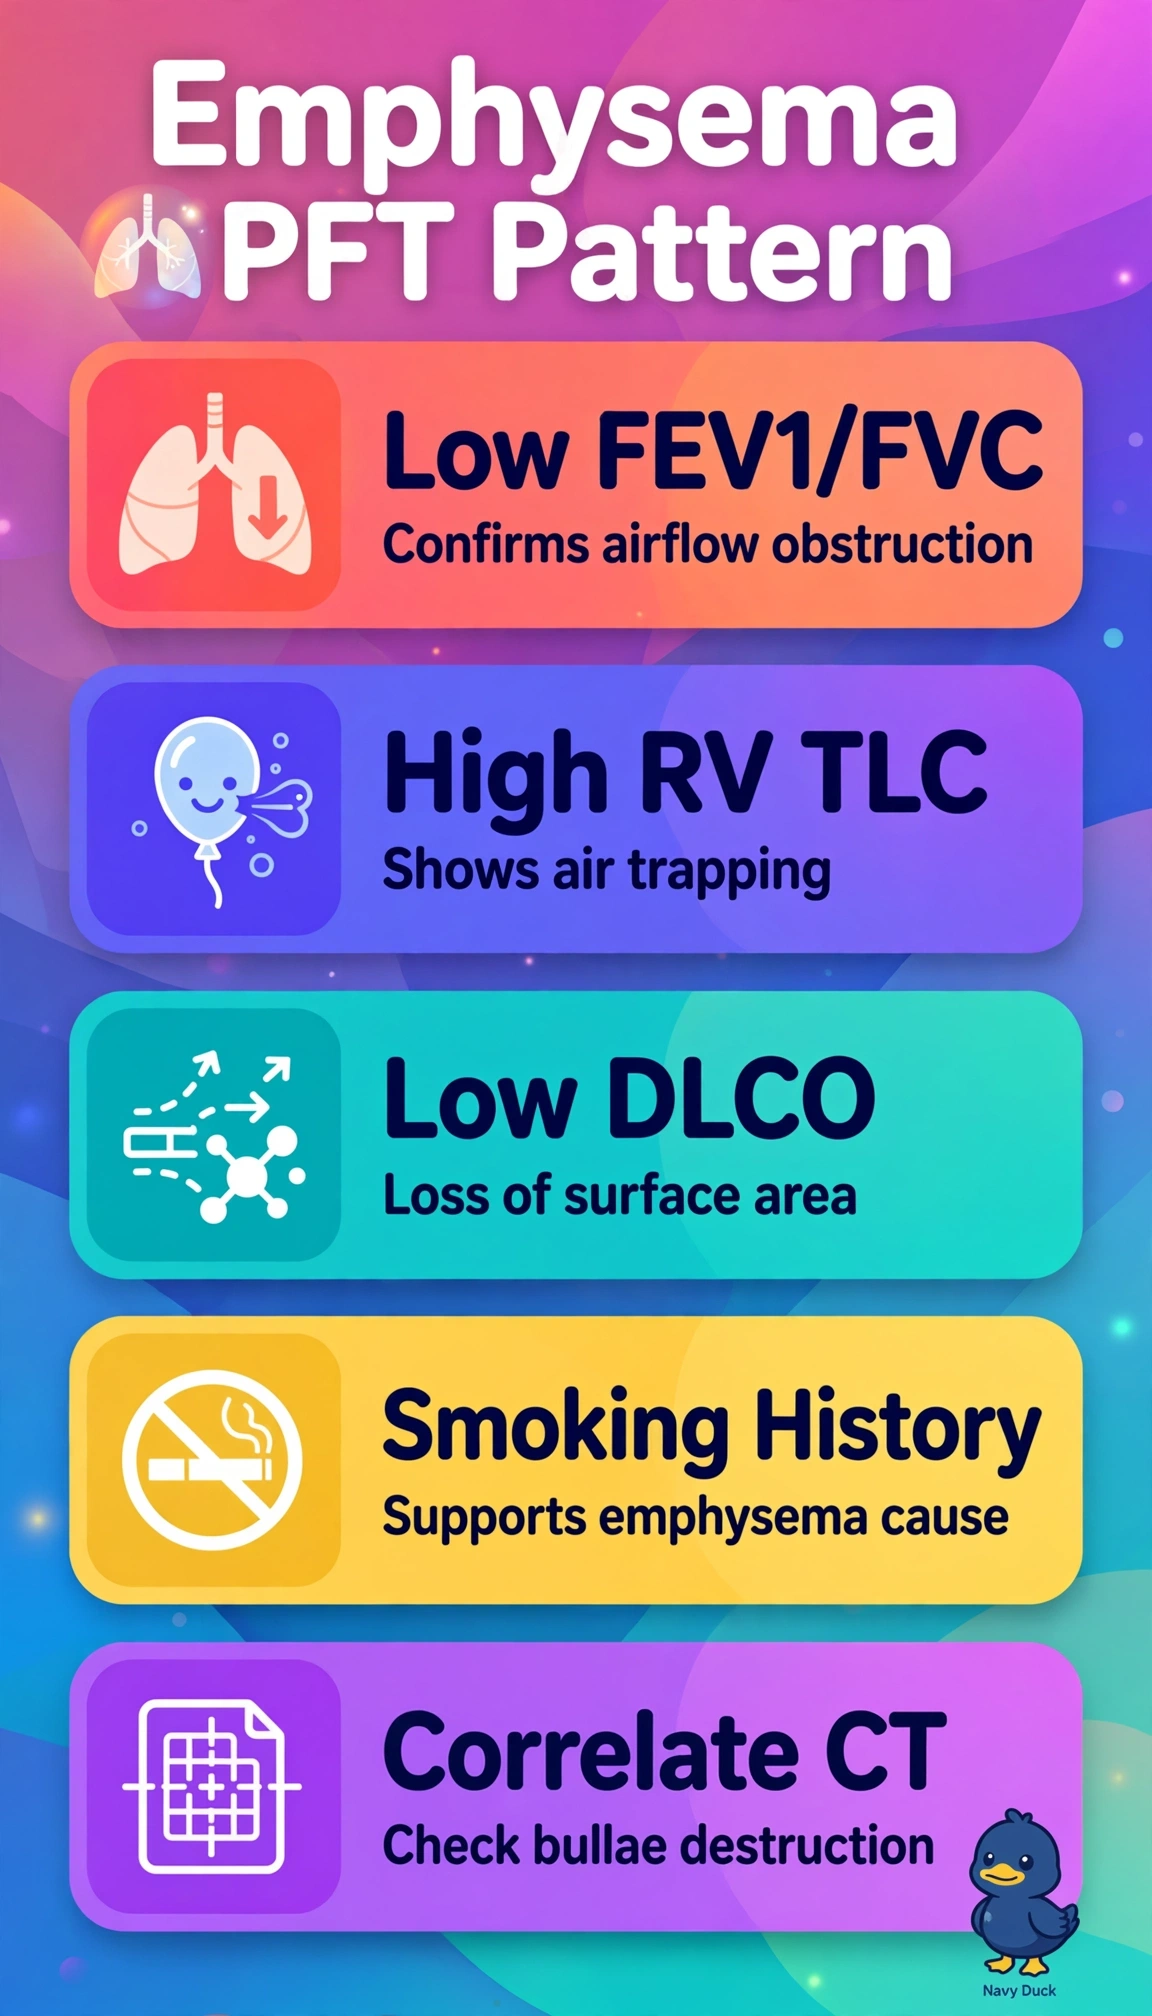
You've got low flow, big lungs, and poor gas transfer staring at you. Emphysema destroys alveolar walls, so air gets trapped and diffusion tanks. That's classic obstruction plus low DLCO.
Full Explanation
A reduced FEV1/FVC ratio defines obstruction, while increased residual volume and total lung capacity indicate hyperinflation and air trapping from loss of elastic recoil, and a reduced DLCO reflects loss of alveolar-capillary surface area, which together point to emphysema rather than airway-only disease. Restrictive pattern interpretation fails because total lung capacity is increased rather than decreased as required for true restriction, even though DLCO can be reduced in fibrosis. Obstructive pattern with preserved diffusion describes chronic bronchitis or asthma where airways are narrowed but alveolar membranes remain intact, so it misses the stated DLCO reduction. Mixed pattern with normal diffusion fails on two counts because volumes show hyperinflation rather than restriction and diffusion is abnormal rather than preserved as seen in uncomplicated asthma. Exam caveat is to link DLCO to parenchymal versus airway disease and always correct interpretation for hemoglobin and lung volume context. Practical check is to correlate PFT pattern with CT morphology, smoking history, and flow-volume loop shape before finalizing the phenotype.