
A 34-year-old with moderate persistent asthma presents with wheezing, prolonged expiration, peak flow 65% of personal best, SpO2 94%, and thick mucus plugging despite good inhaler technique. The patient uses albuterol frequently without controller therapy. Which pharmacologic care-plan change best recommends bronchodilators, anti-inflammatories, mucolytics, and vasodilators?
Select an answer to reveal the explanation.
Short Explanation
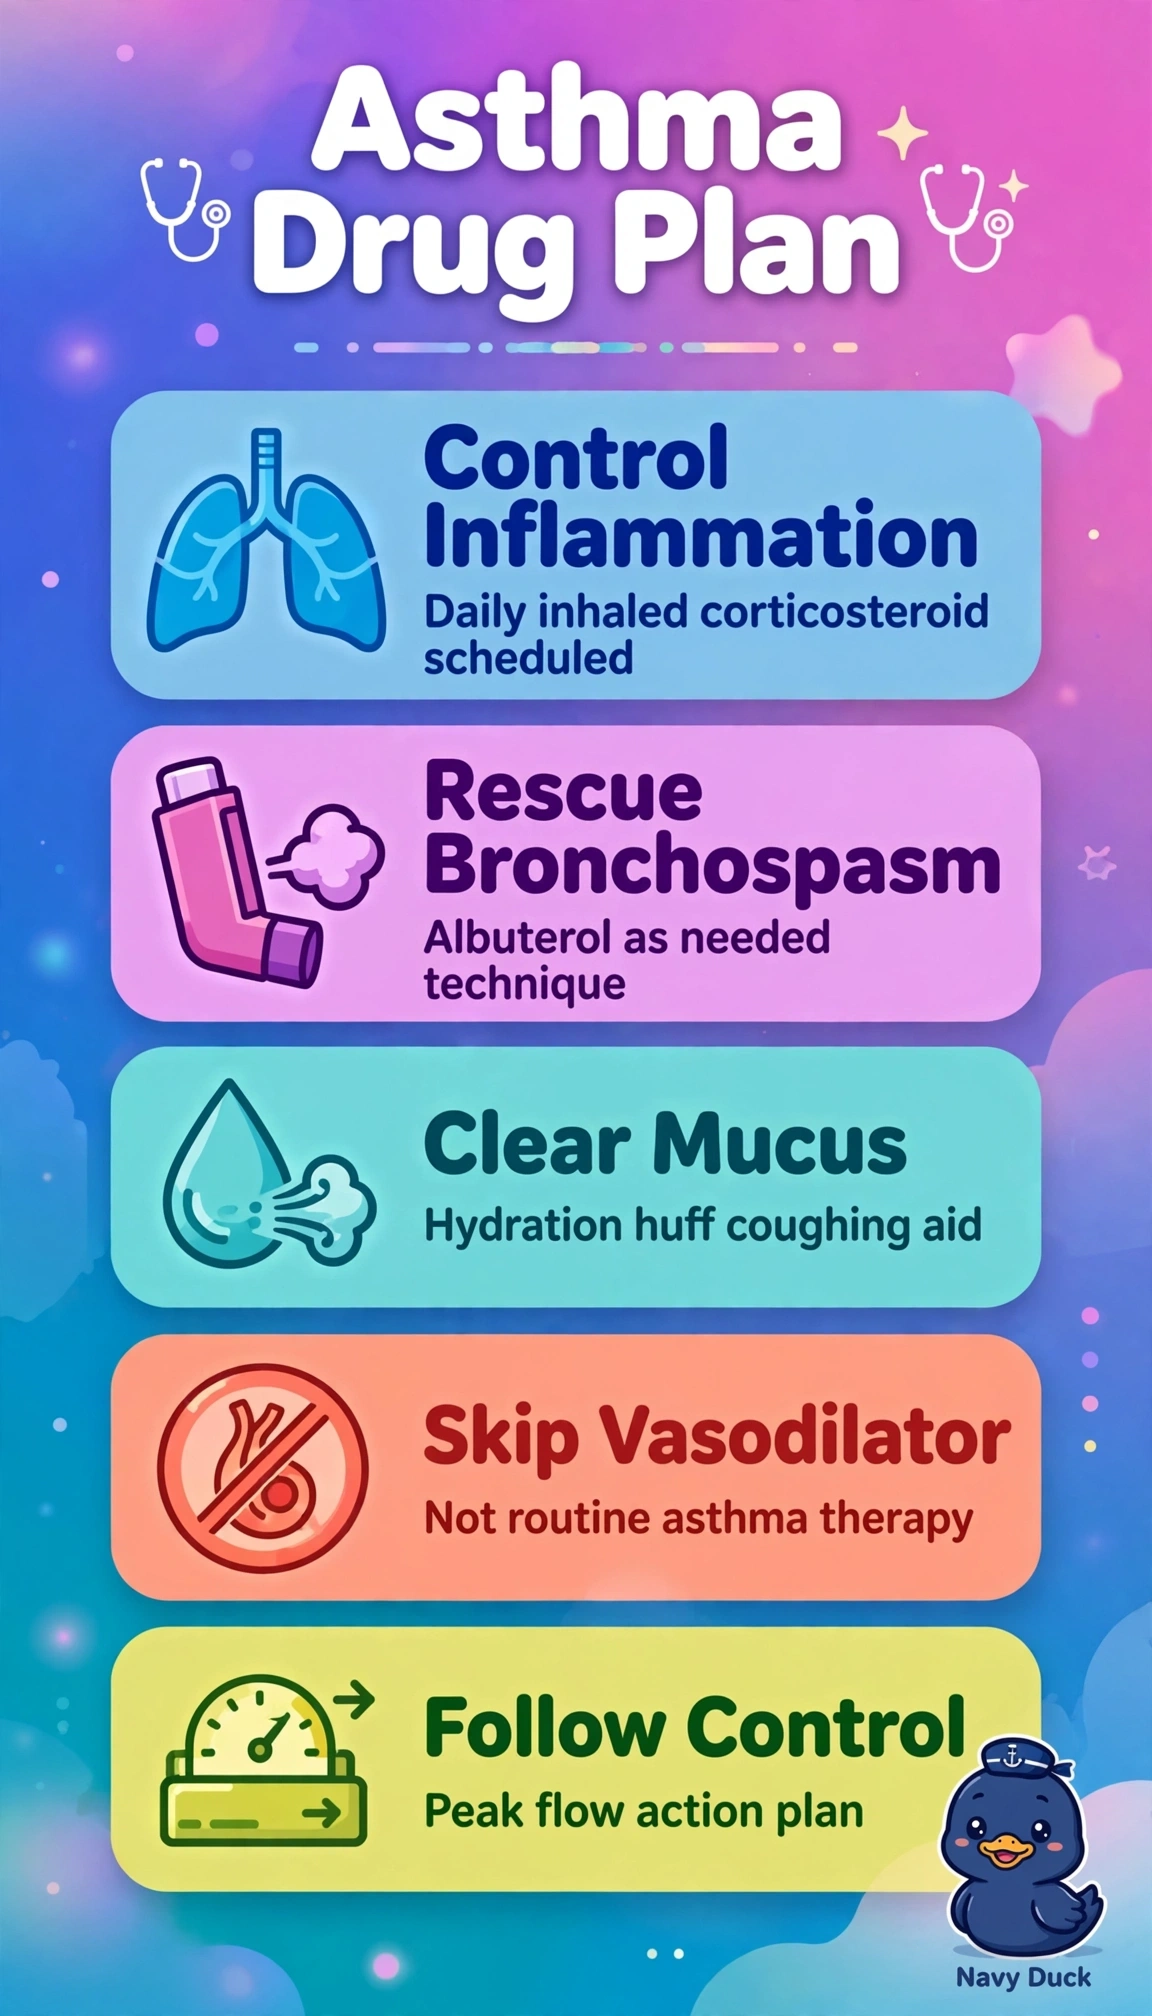
You're dealing with swollen, twitchy airways, so you'll want a daily controller to cool things down, not just quick puffs when you're tight — it's like turning down the stove instead of just opening a window. Your best move is a scheduled inhaled corticosteroid with as-needed albuterol plus clearance, and you can skip routine vasodilators since they don't touch the real problem.
Full Explanation
The correct plan fits moderate persistent asthma with frequent rescue use, wheezing, prolonged expiration, peak flow 65% indicating poor control, and SpO2 94% with mucus plugging despite good technique, so daily inhaled corticosteroid suppresses airway inflammation and hyperresponsiveness while as-needed albuterol preserves acute bronchodilation, airway clearance addresses secretions, and no routine vasodilator is indicated because mild desaturation does not equal pulmonary hypertension. The scheduled corticosteroid plus scheduled salmeterol without rescue fails acute bronchodilation because maintenance long-acting agonists cannot relieve sudden bronchospasm and guidelines require accessible short-acting relief even when control is optimized. The tiotropium plus as-needed albuterol without corticosteroid fails anti-inflammatory control because anticholinergic maintenance borrowed from COPD does not suppress eosinophilic inflammation driving persistent asthma and exacerbations. The corticosteroid plus albuterol plus routine oral sildenafil fails vasodilator stewardship because systemic vasodilation borrowed from hypertension care does not relieve wheezing or plugging at SpO2 94% and risks hypotension. Exam caveat is to avoid transferring COPD or hypertension protocols to asthma and recall 50-80% of personal best defines yellow zone needing controller step-up, not critical care vasodilators. Practical check is to verify adherence, technique and triggers, provide written action plan with peak flow diary, and schedule spirometry follow-up.