
A public-health chatbot must stay inside clinic conversation budget limits. What should ops track?
Select an answer to reveal the explanation.
Short Explanation
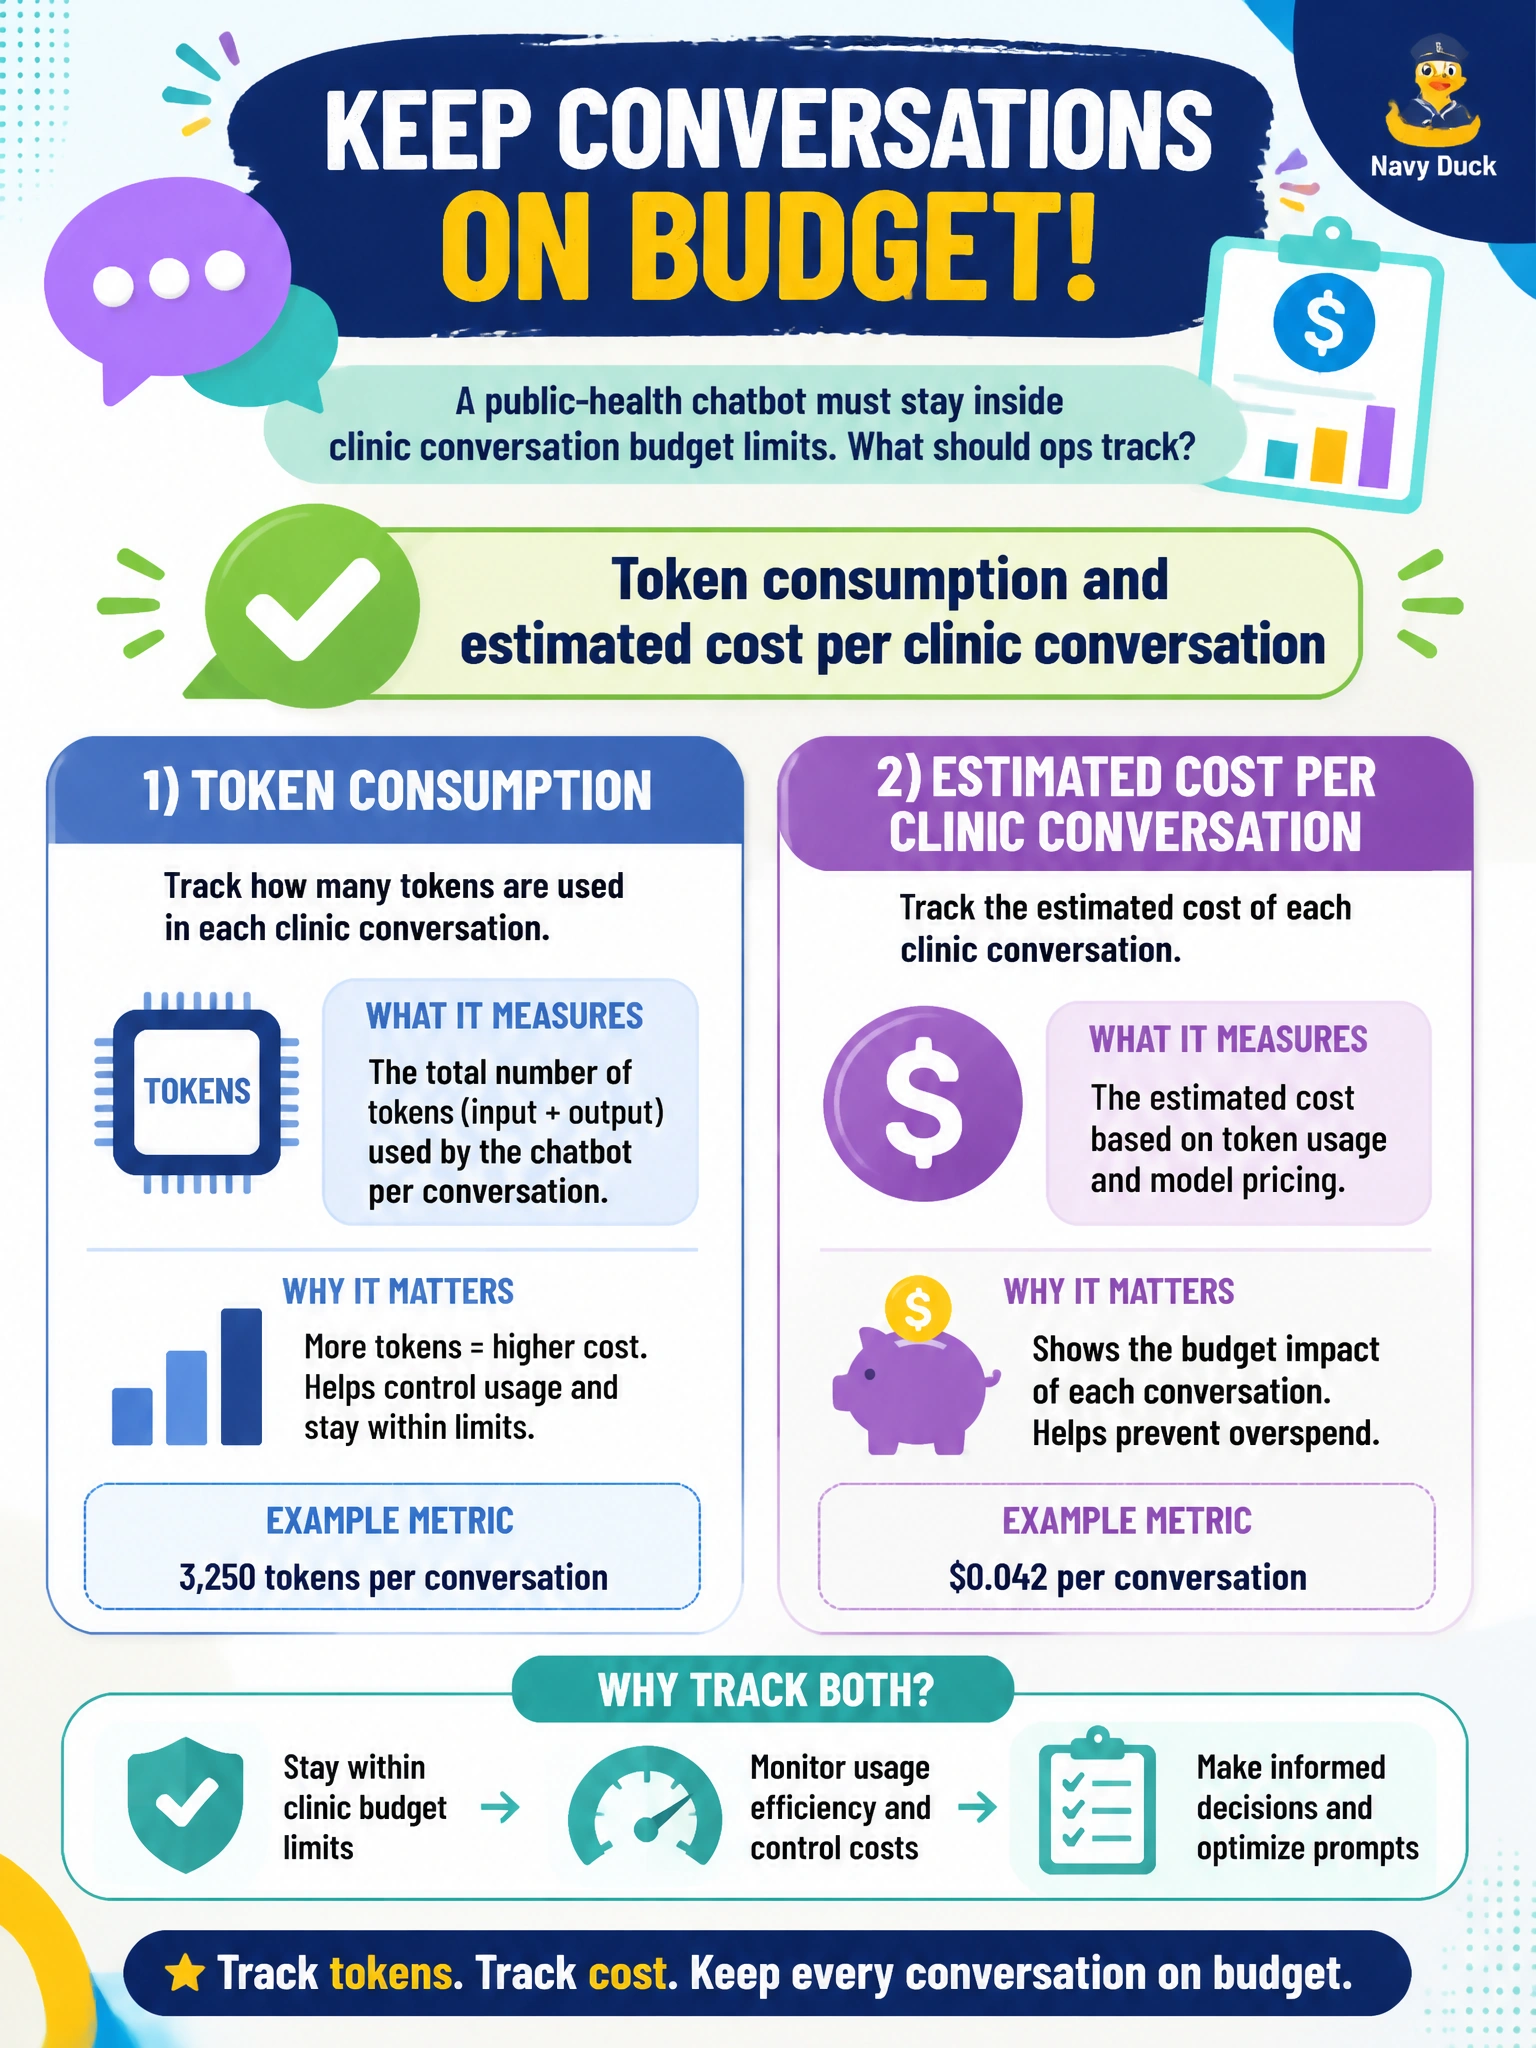
Clinic budgets care about dollars per chat. Track tokens and estimated cost per conversation so spend stays visible.
Full Explanation
Tracking token consumption and estimated cost per clinic conversation is correct because generative cost observability centers on tokens and the spend they drive. A public-health chatbot constrained by clinic conversation budget limits needs per-conversation token and cost telemetry so ops can see whether average and tail spend stay inside appropriations. That view supports prompt trimming, model-tier choices, caching, and conversation-length policies without waiting for the monthly invoice surprise.
Invoice totals and billed amounts per clinic department usage arrive too late and too coarse to manage a budget in real time—by the time the invoice lands, the clinic still cannot see which individual conversations drove the spend or intervene before the appropriation is exceeded.
Token consumption and estimated cost per clinic chatbot instance track spend at the instance level but stay too coarse to manage a conversation budget—without a per-conversation breakdown, ops cannot see which individual conversations drove the spend or intervene before the appropriation is exceeded.
Token quotas and rate limits per clinic conversation budget set enforcement guardrails but do not track actual spend—without per-conversation token and cost telemetry, ops cannot observe average and tail cost efficiency against clinic appropriations.
Exam caveat: cost observability for GenAI = tokens + estimated/actual cost, ideally normalized per conversation, session, or successful resolution. Budget-limit stems point to token/cost tracking, not department-level invoice totals and billed amounts, instance-level token/cost aggregates, or quota/limit settings without actual spend observability.
Operational check: emit token usage per clinic conversation, estimate cost from model pricing, dashboard average and p95 cost-per-conversation against the clinic budget, alert before monthly appropriation burn, and A/B shorter system prompts or cheaper models when cost trends breach the limit while quality remains acceptable.
Prefer to study offline? Printable PDF study book + test engine ($7.50, unofficial). These questions stay free here.