
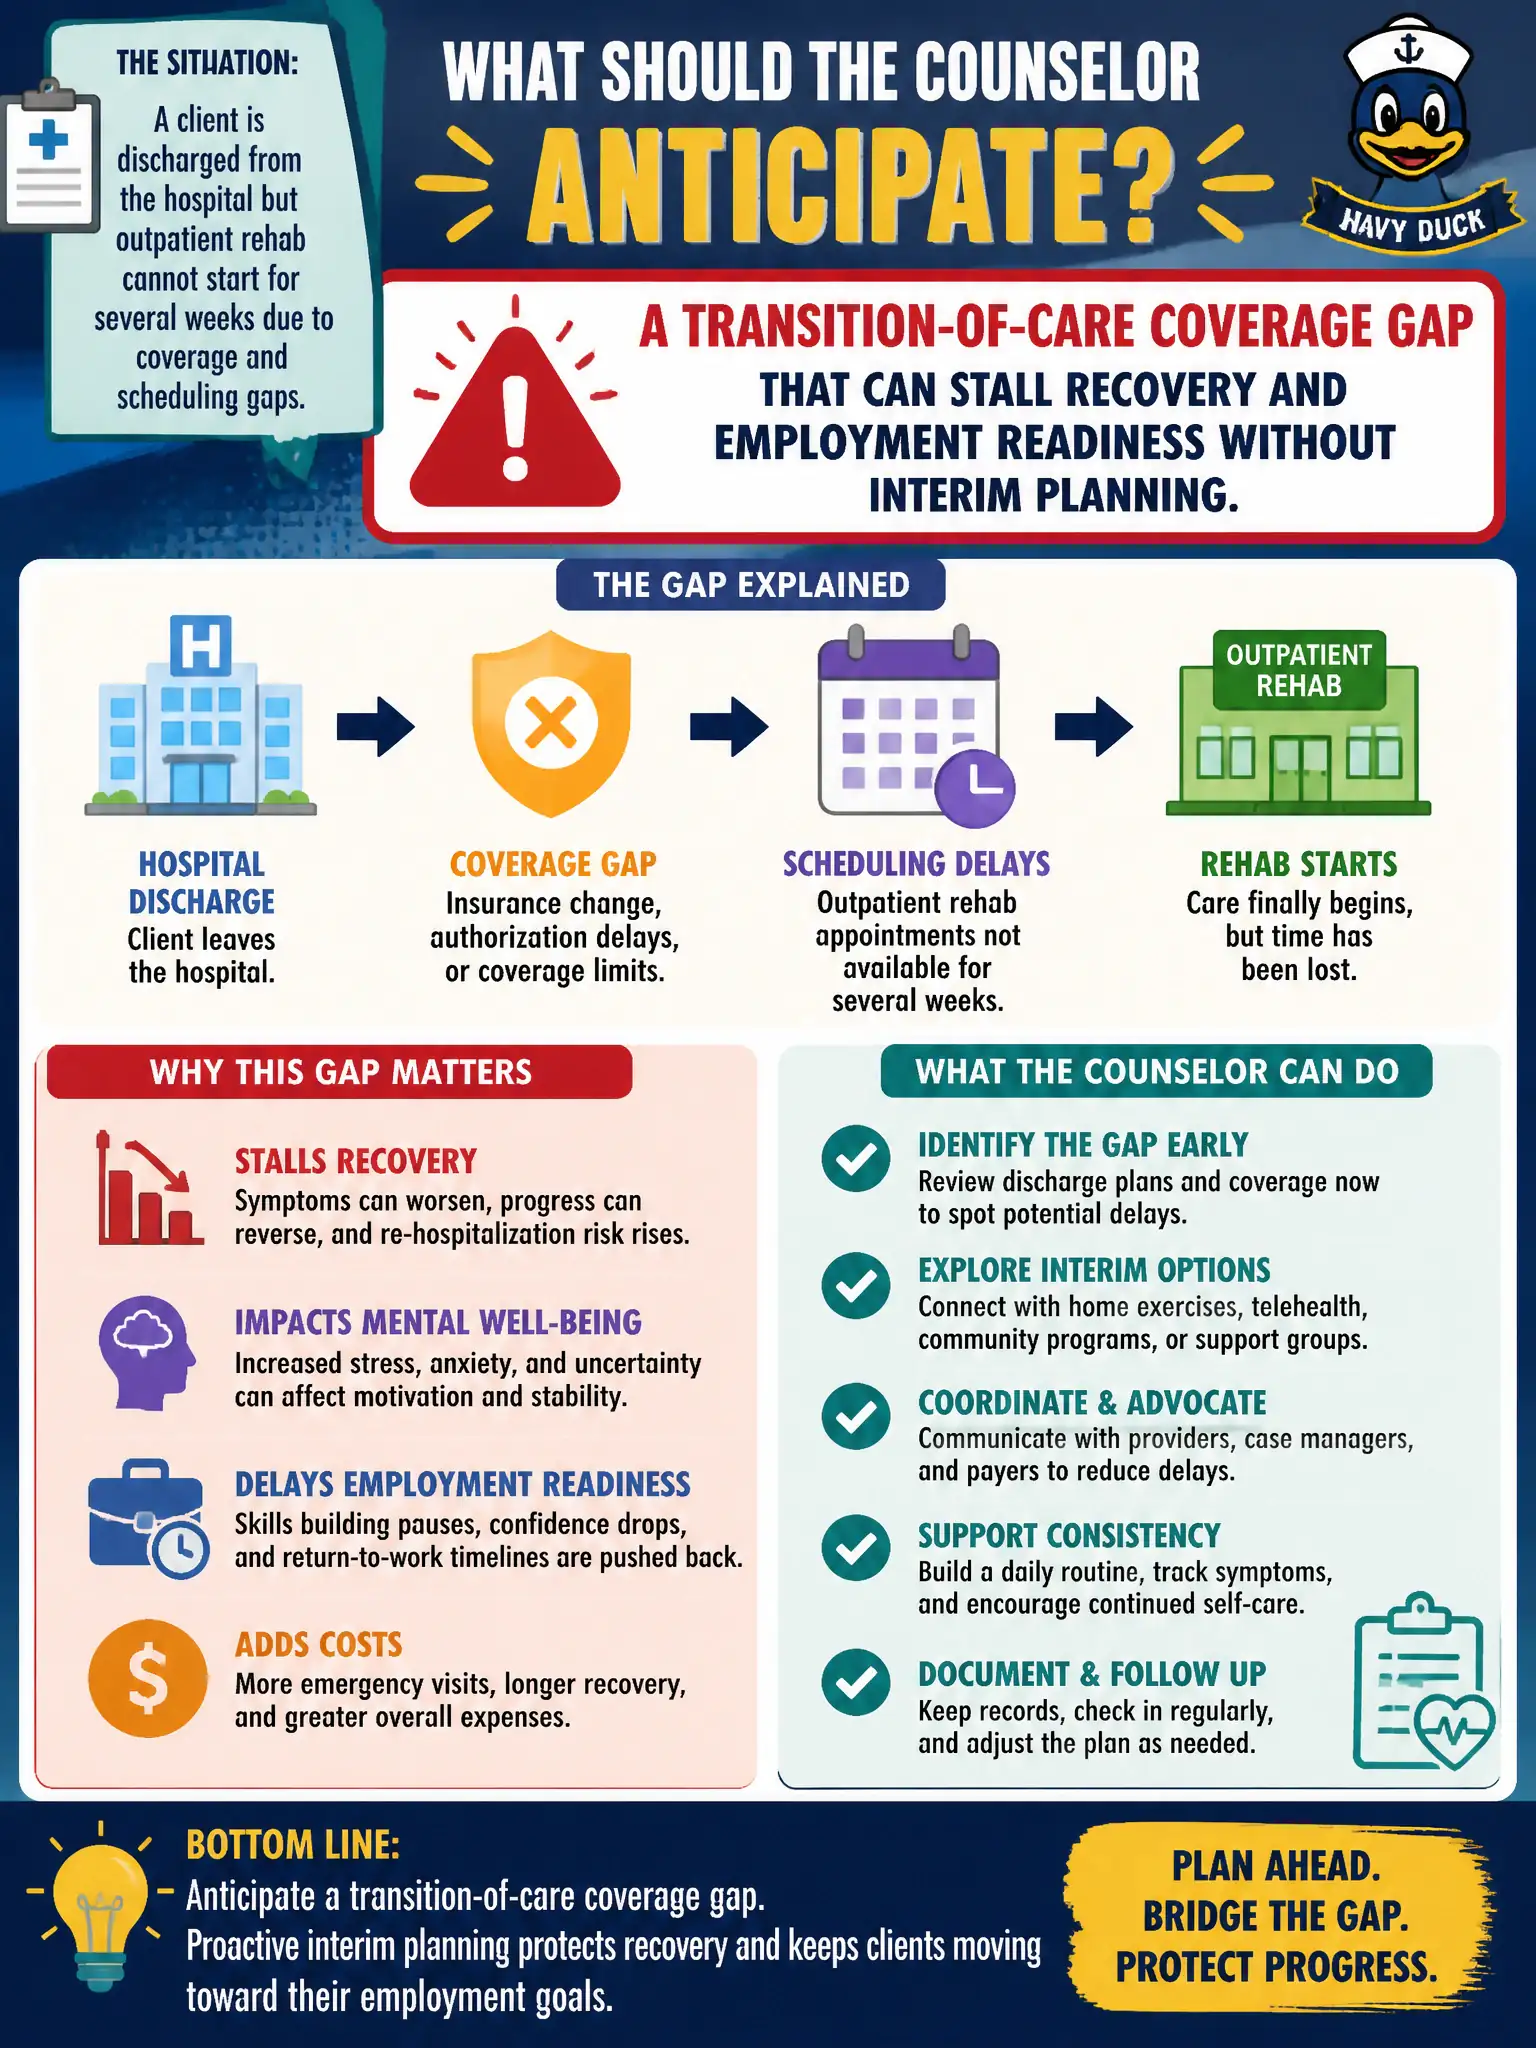
A client is discharged from the hospital but outpatient rehab cannot start for several weeks due to coverage and scheduling gaps. What should the counselor anticipate?
Select an answer to reveal the explanation.
Short Explanation
The hospital door closes and the outpatient door isn't open yet—that's a ditch, not a driveway. Expect the gap, build a bridge (interim supports, advocacy, temporary plans). Don't pretend discharge equals 'fully back.
Full Explanation
Hospital discharge followed by weeks of delay before outpatient rehab starts often signals a transition-of-care coverage and scheduling gap that can stall recovery and employment readiness without interim planning. Municipal CRCs should anticipate that gap, arrange bridging supports, and adjust vocational timelines rather than assume seamless continuum of care. Same-day unlimited outpatient rehab is not guaranteed by discharge paperwork. Believing hospital discharge always guarantees same-day unlimited outpatient rehab ignores authorization, network, and capacity constraints. Claiming gaps between inpatient and outpatient care never affect vocational timelines denies a common civic case risk. Abandoning employment goals until all insurance issues resolve years later overreacts; interim planning can keep goals alive while coverage is sorted. Exam caveat: gap length and remedies vary by payer and locality; the examinable skill is anticipating transition risk and planning interim function supports. Operational check: at discharge planning, verify outpatient start date and authorization status, identify coverage or scheduling gaps, put interim home/community supports or light vocational maintenance tasks in place, and calendar a follow-up before the gap becomes an unmonitored stall.