
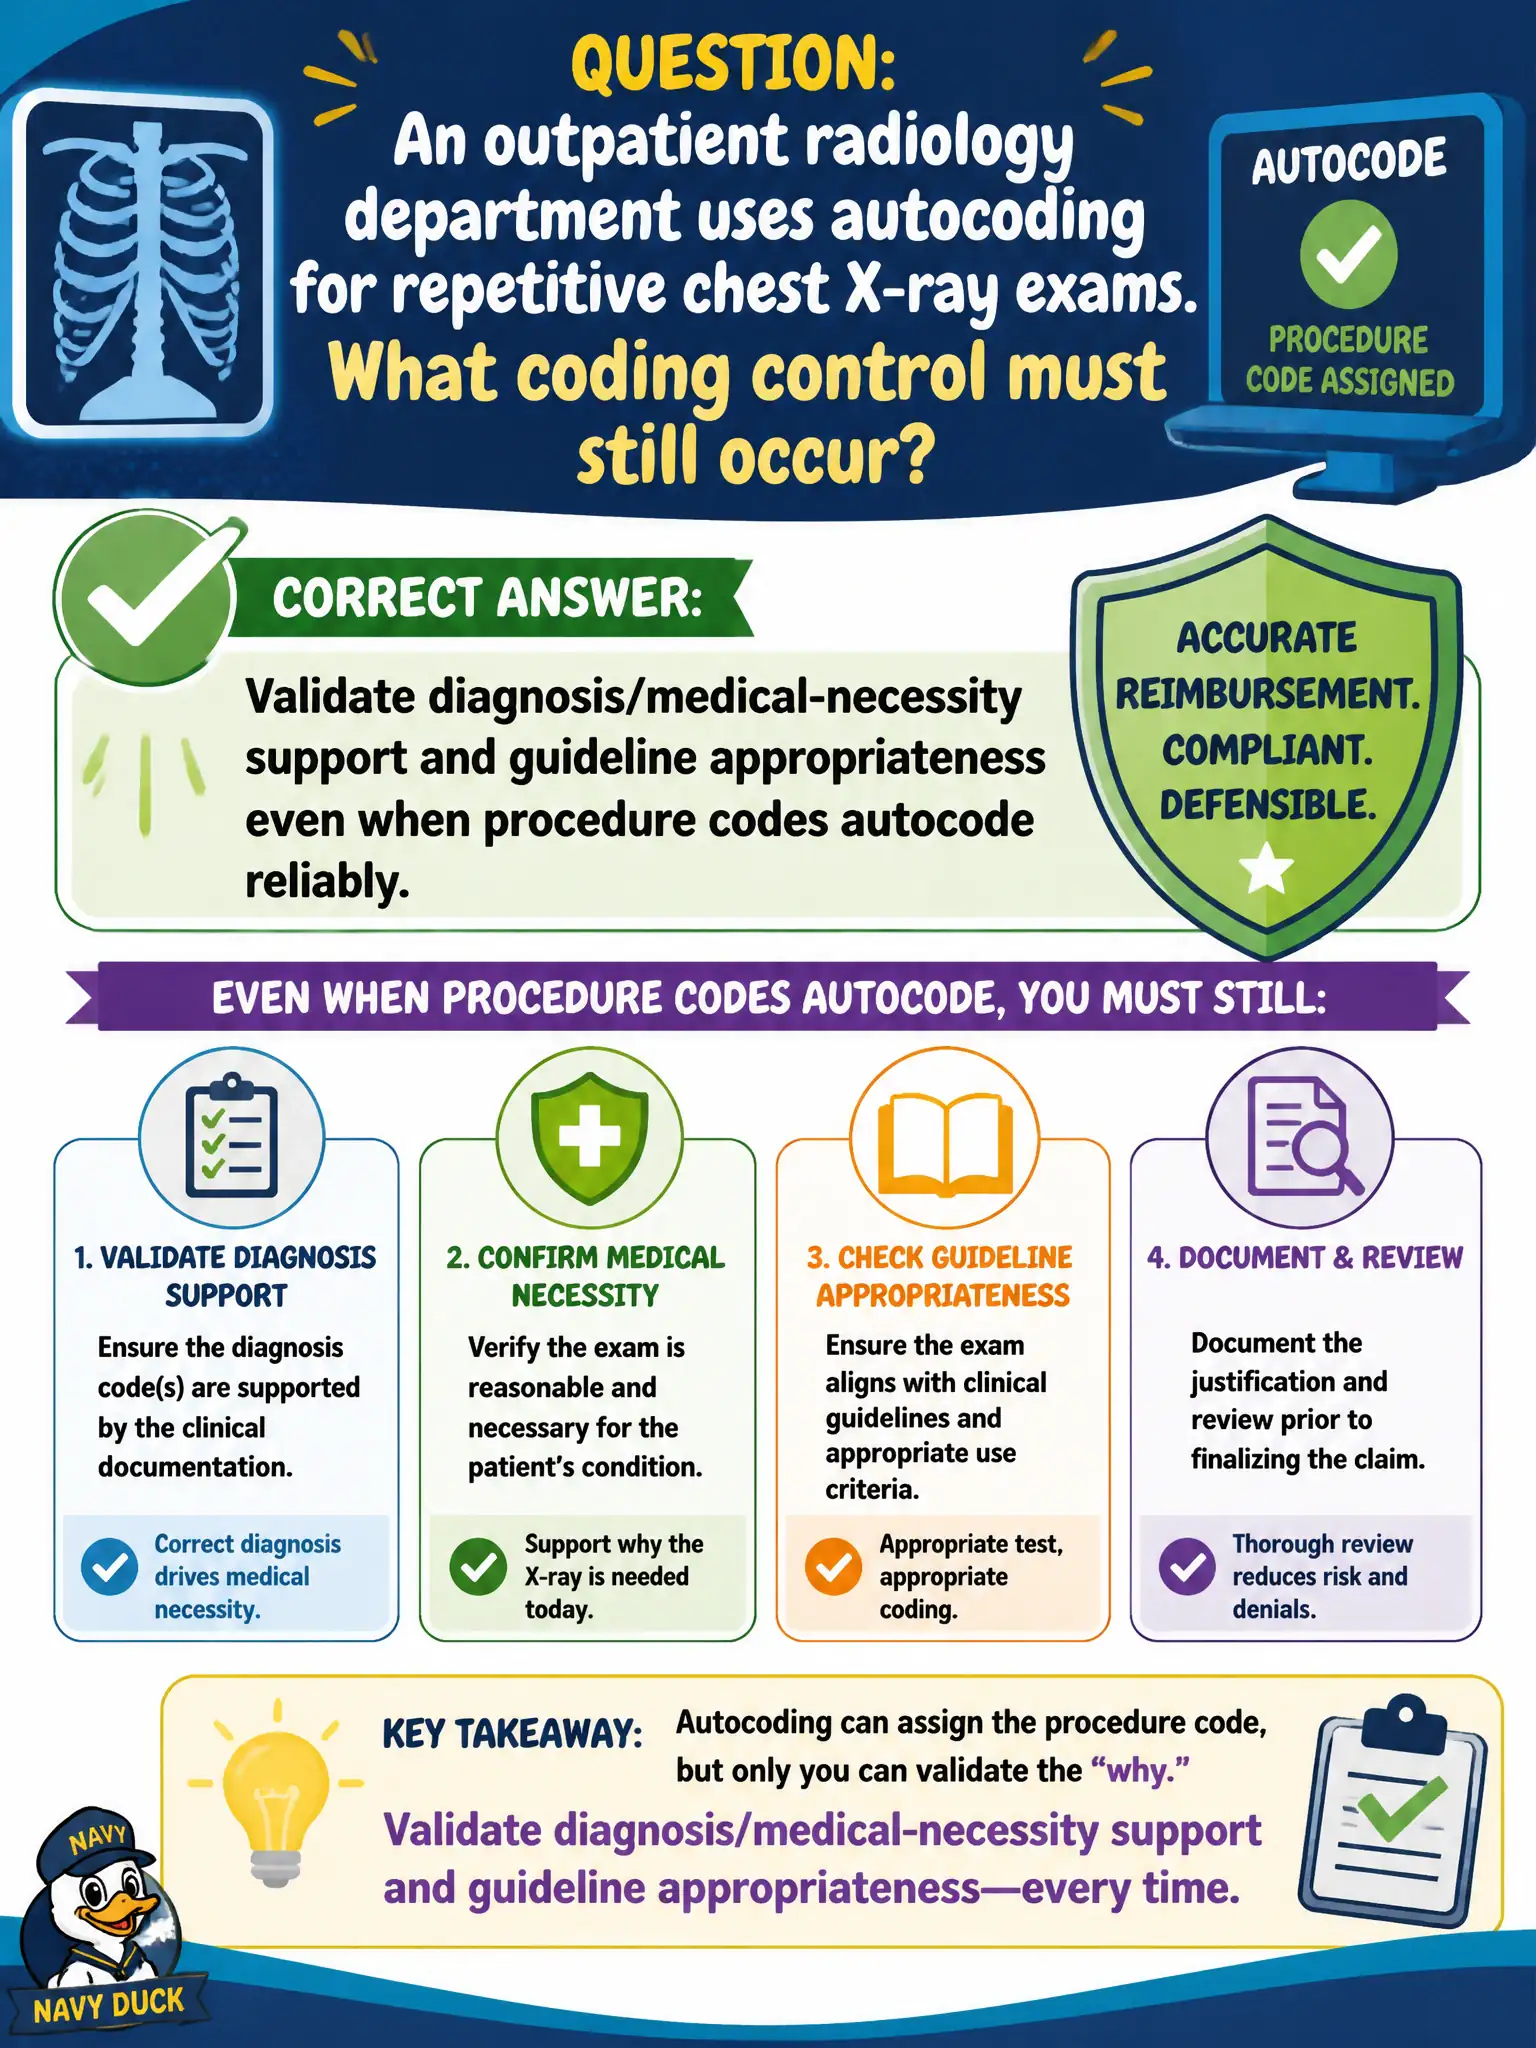
An outpatient radiology department uses autocoding for repetitive chest X-ray exams. What coding control must still occur?
Select an answer to reveal the explanation.
Short Explanation
Autocoding the X-ray CPT is the easy part—like stamping the same ticket all day. You still have to check that the diagnosis and necessity story on that ticket actually makes sense.
Full Explanation
An outpatient radiology department in a county hospital that uses autocoding for repetitive chest X-ray exams must still validate diagnosis and medical-necessity support and guideline appropriateness even when procedure codes autocode reliably. Civic outpatient integrity covers why the test was done, not only which CPT stamped out. Skipping diagnosis review because repetitive exams never require medical necessity on facility claims is false. Accepting whatever CAC posts for both CPT and ICD without opening the order or report abandons validation. Converting all radiology claims to inpatient MS-DRGs to avoid outpatient necessity edits falsifies setting. Exam caveat: autocoding procedures does not autocertify diagnosis or necessity. Operational check: review order indications and report impressions, confirm ICD support for the service, correct mismatched diagnosis codes, and sample autocoded radiology claims in outpatient coding audits. Treat encoders, groupers, and CAC as assistants inside civic HIM: useful for speed, never a substitute for documentation review, Official Guidelines, or PHI safeguards. Re-read the authenticated record before finalizing whenever tools, payers, or dashboards push a result the documentation does not support.