
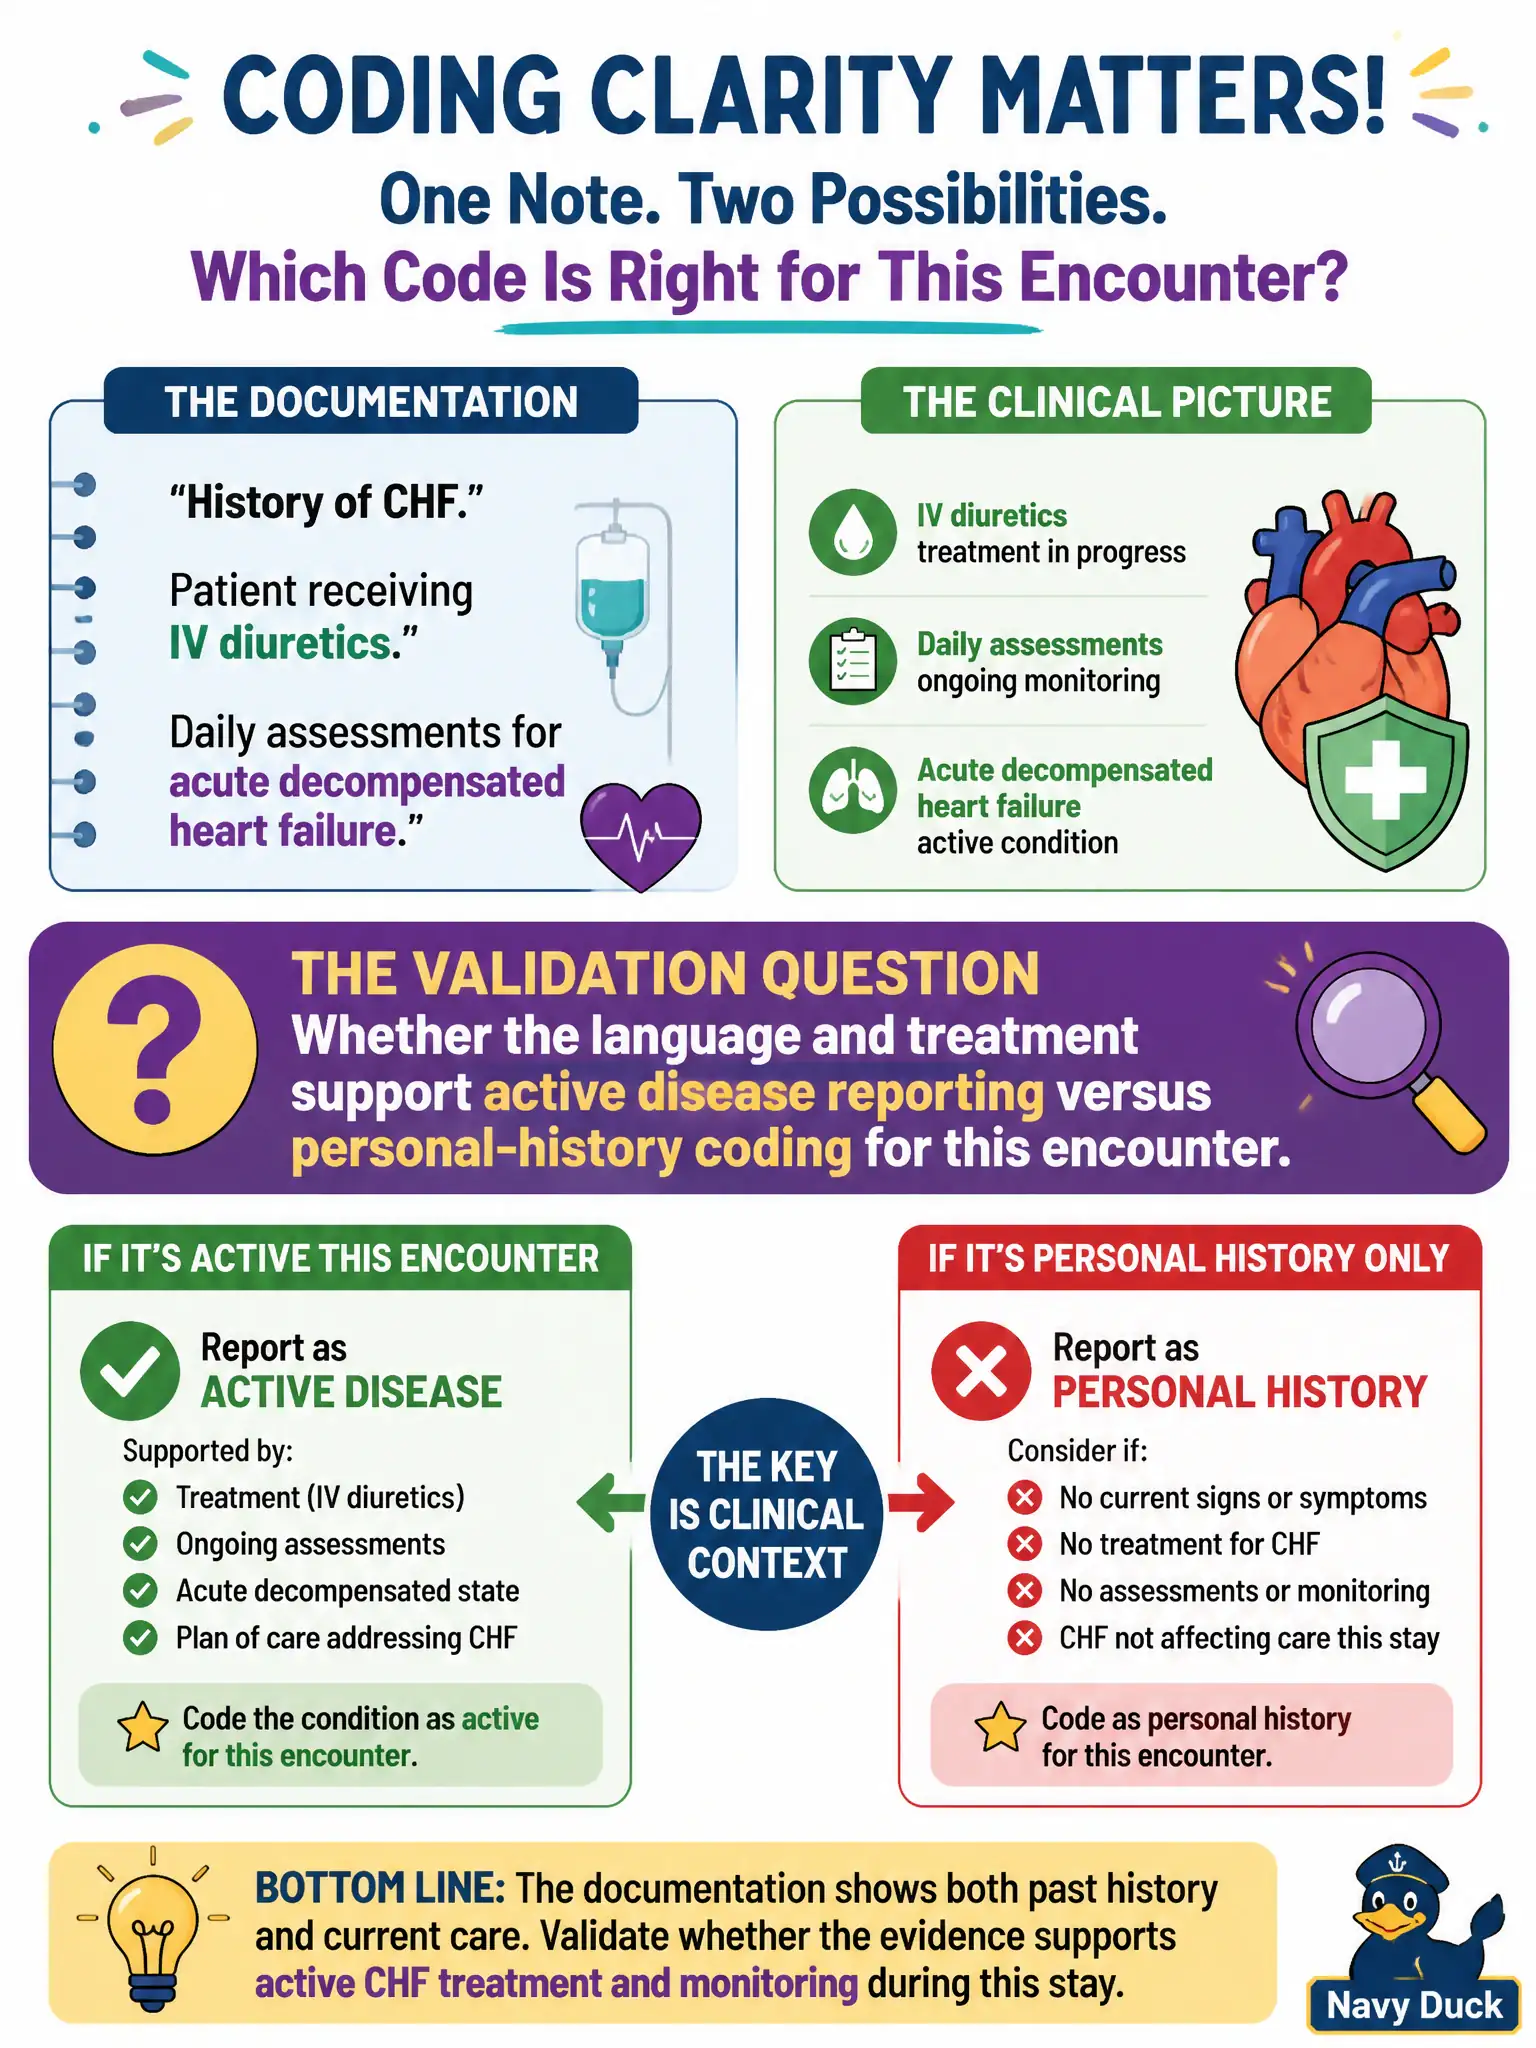
Documentation mixes 'history of CHF' in one note with ongoing IV diuretics and daily assessments for acute decompensated heart failure during the stay. What validation question should the hospital coder resolve?
Select an answer to reveal the explanation.
Short Explanation
History-of language and active treatment can talk past each other. If the team is still pushing IV diuretics for decompensated failure, 'history of' may be leftover phrasing. Validate acuity against what was actually managed this stay.
Full Explanation
Mixed documentation that says 'history of CHF' in one place while describing ongoing IV diuretics and daily assessments for acute decompensated heart failure forces a validation question: do language and treatment support active disease reporting for this encounter, or only personal-history coding? Coders resolve that conflict by weighing contemporaneous diagnostic statements and therapeutic interventions against mere historical labels, querying when the status remains ambiguous. Whether coding software prefers Z-codes for cardiac conditions is a tool bias, not a clinical validation standard. Nursing acuity scores alone do not establish principal diagnosis under UHDDS rules. A payer's preferred synonym list cannot redefine whether disease is active versus historical in the legal record. Exam caveat: acute-on-chronic heart failure, systolic/diastolic specificity, and history-of codes are frequently tested; do not let copy-forward 'history of' language automatically suppress clearly treated acute decompensation. Operational check: list the conflicting phrases, match them to treatments and assessments during the stay, and assign active versus history codes—or query—based on the validated encounter status for the municipal hospital abstract.