
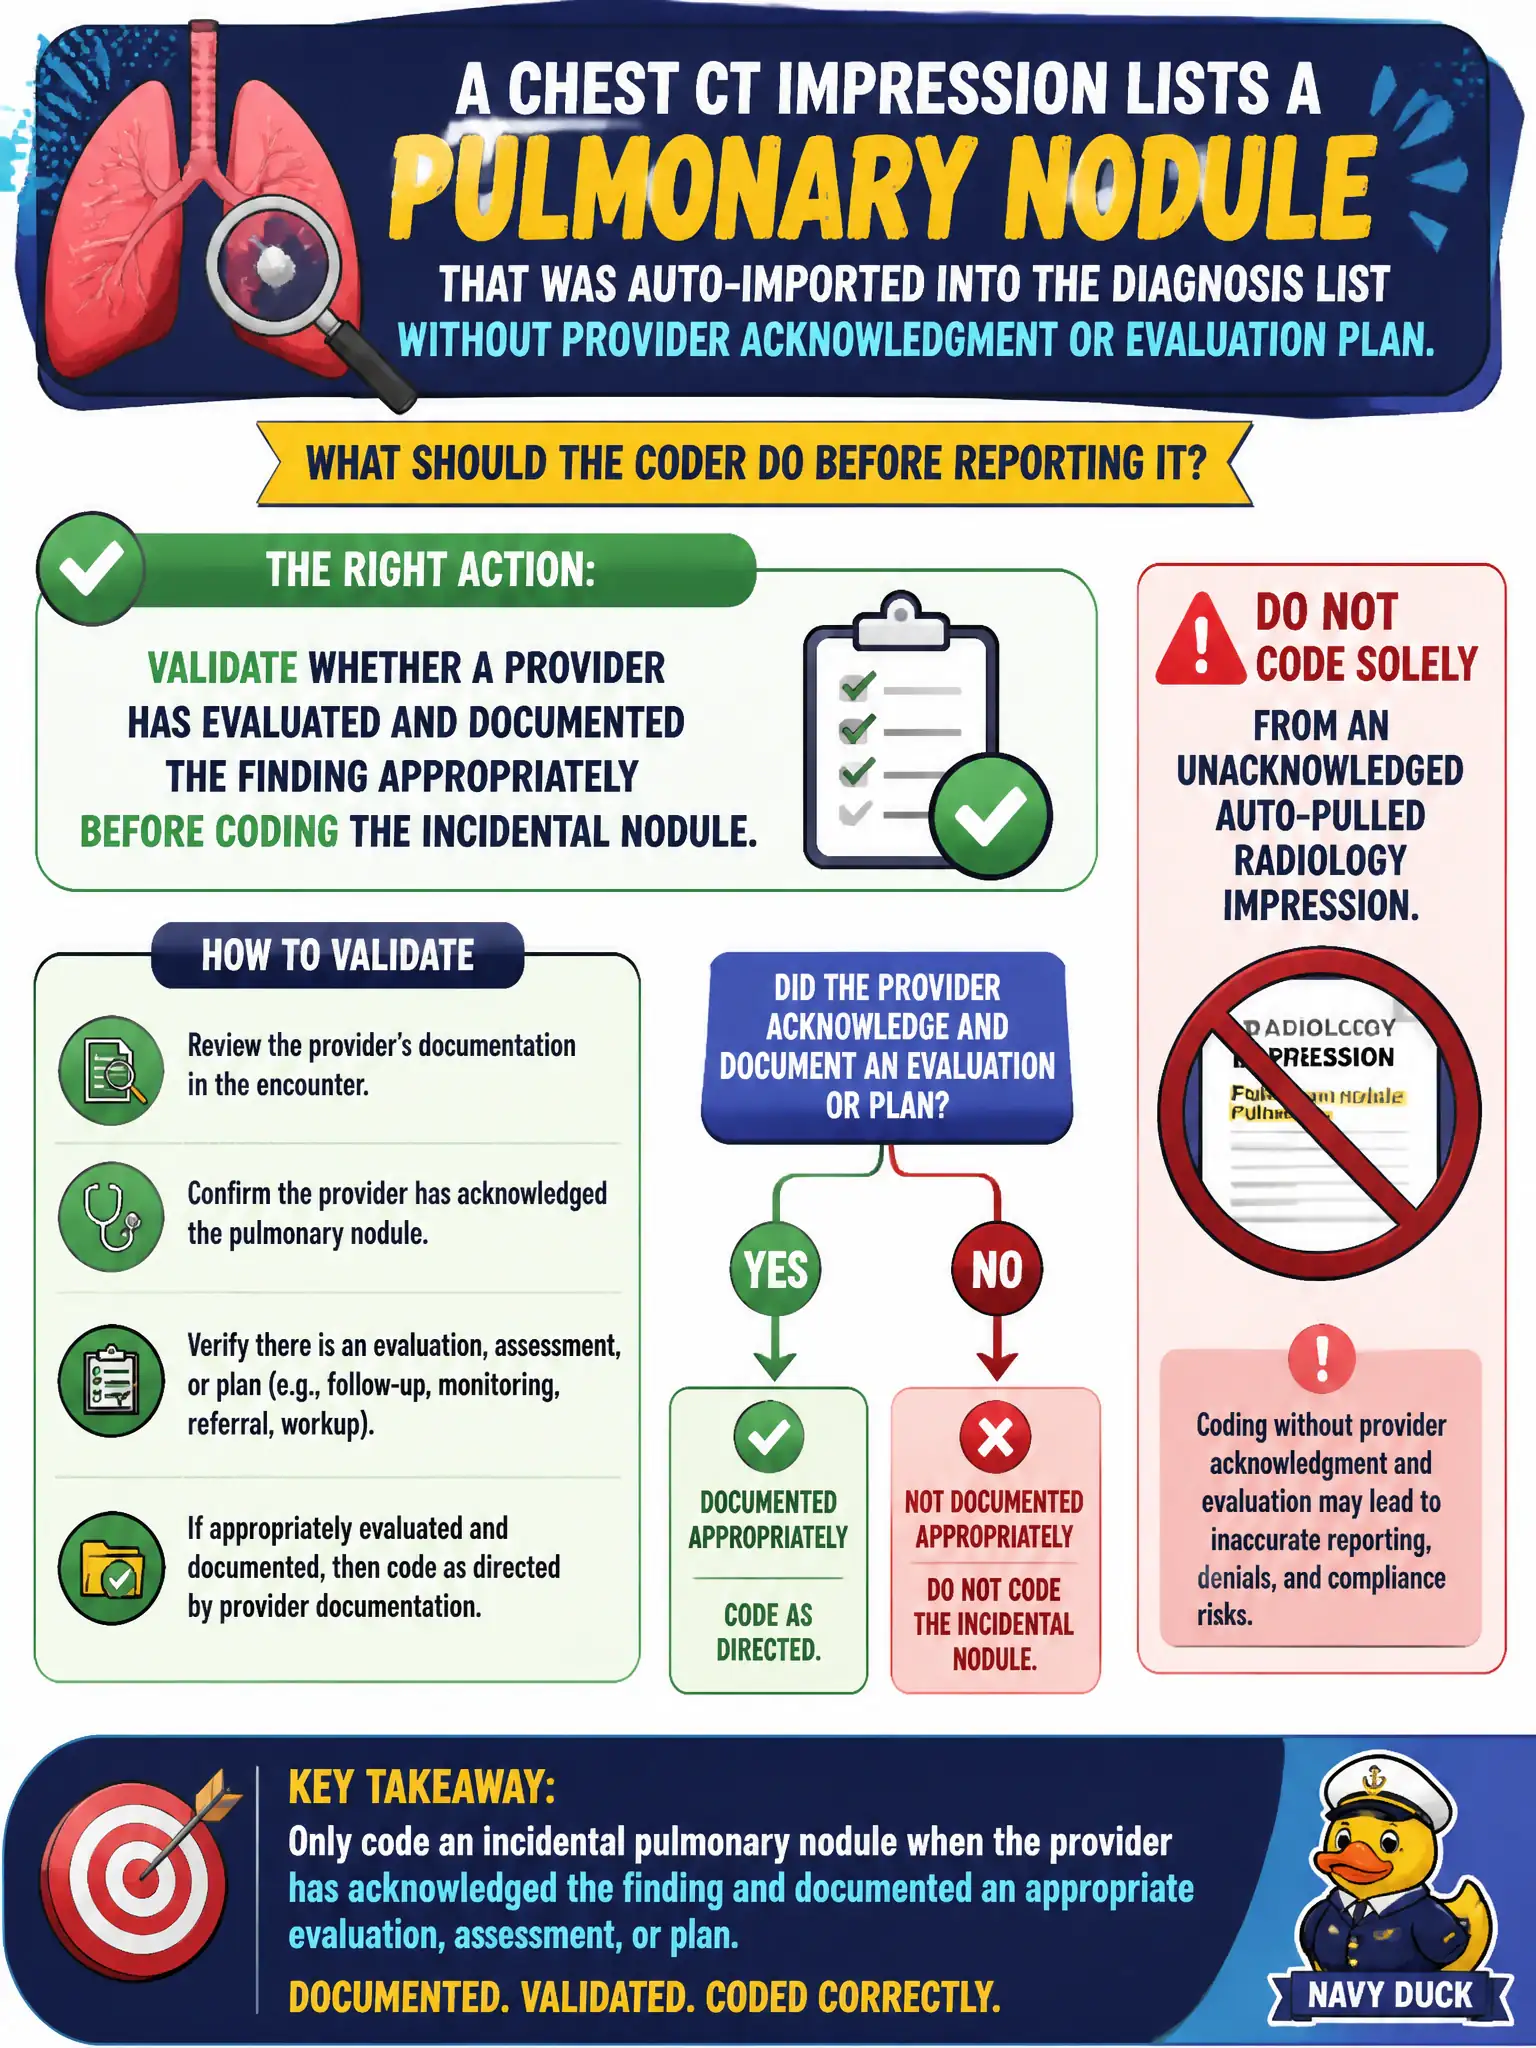
A chest CT impression lists a pulmonary nodule that was auto-imported into the diagnosis list without provider acknowledgment or evaluation plan. What should the coder do before reporting it?
Select an answer to reveal the explanation.
Short Explanation
Auto-import is not the same as a doctor owning the finding. An incidental nodule sitting in a worklist dump should not hop onto the coded set by itself. Wait for provider evaluation or documentation that makes it reportable for the encounter.
Full Explanation
Incidental radiology findings auto-imported into a diagnosis list without provider acknowledgment are a common EHR integrity trap. Before reporting a pulmonary nodule from a chest CT impression that was auto-pulled without evaluation or plan, the coder should validate whether a provider has evaluated and documented the finding appropriately; coding solely from an unacknowledged auto-imported impression is inappropriate. Always coding every radiology impression as a secondary diagnosis floods the abstract with unaddressed findings and violates reportable-diagnosis principles. Coding the nodule as malignant neoplasm pending biopsy invents histology the record does not support. Deleting the radiology report to avoid the issue falsifies the legal record rather than resolving documentation. Exam caveat: abnormal findings may be reportable when clinically evaluated, treated, or further studied per UHDDS concepts—but auto-import without provider engagement is not evaluation. Operational check for county imaging-heavy stays: confirm provider acknowledgment or clinical engagement with the nodule in notes or the discharge summary before assigning the diagnosis code; otherwise omit or query per facility policy.