
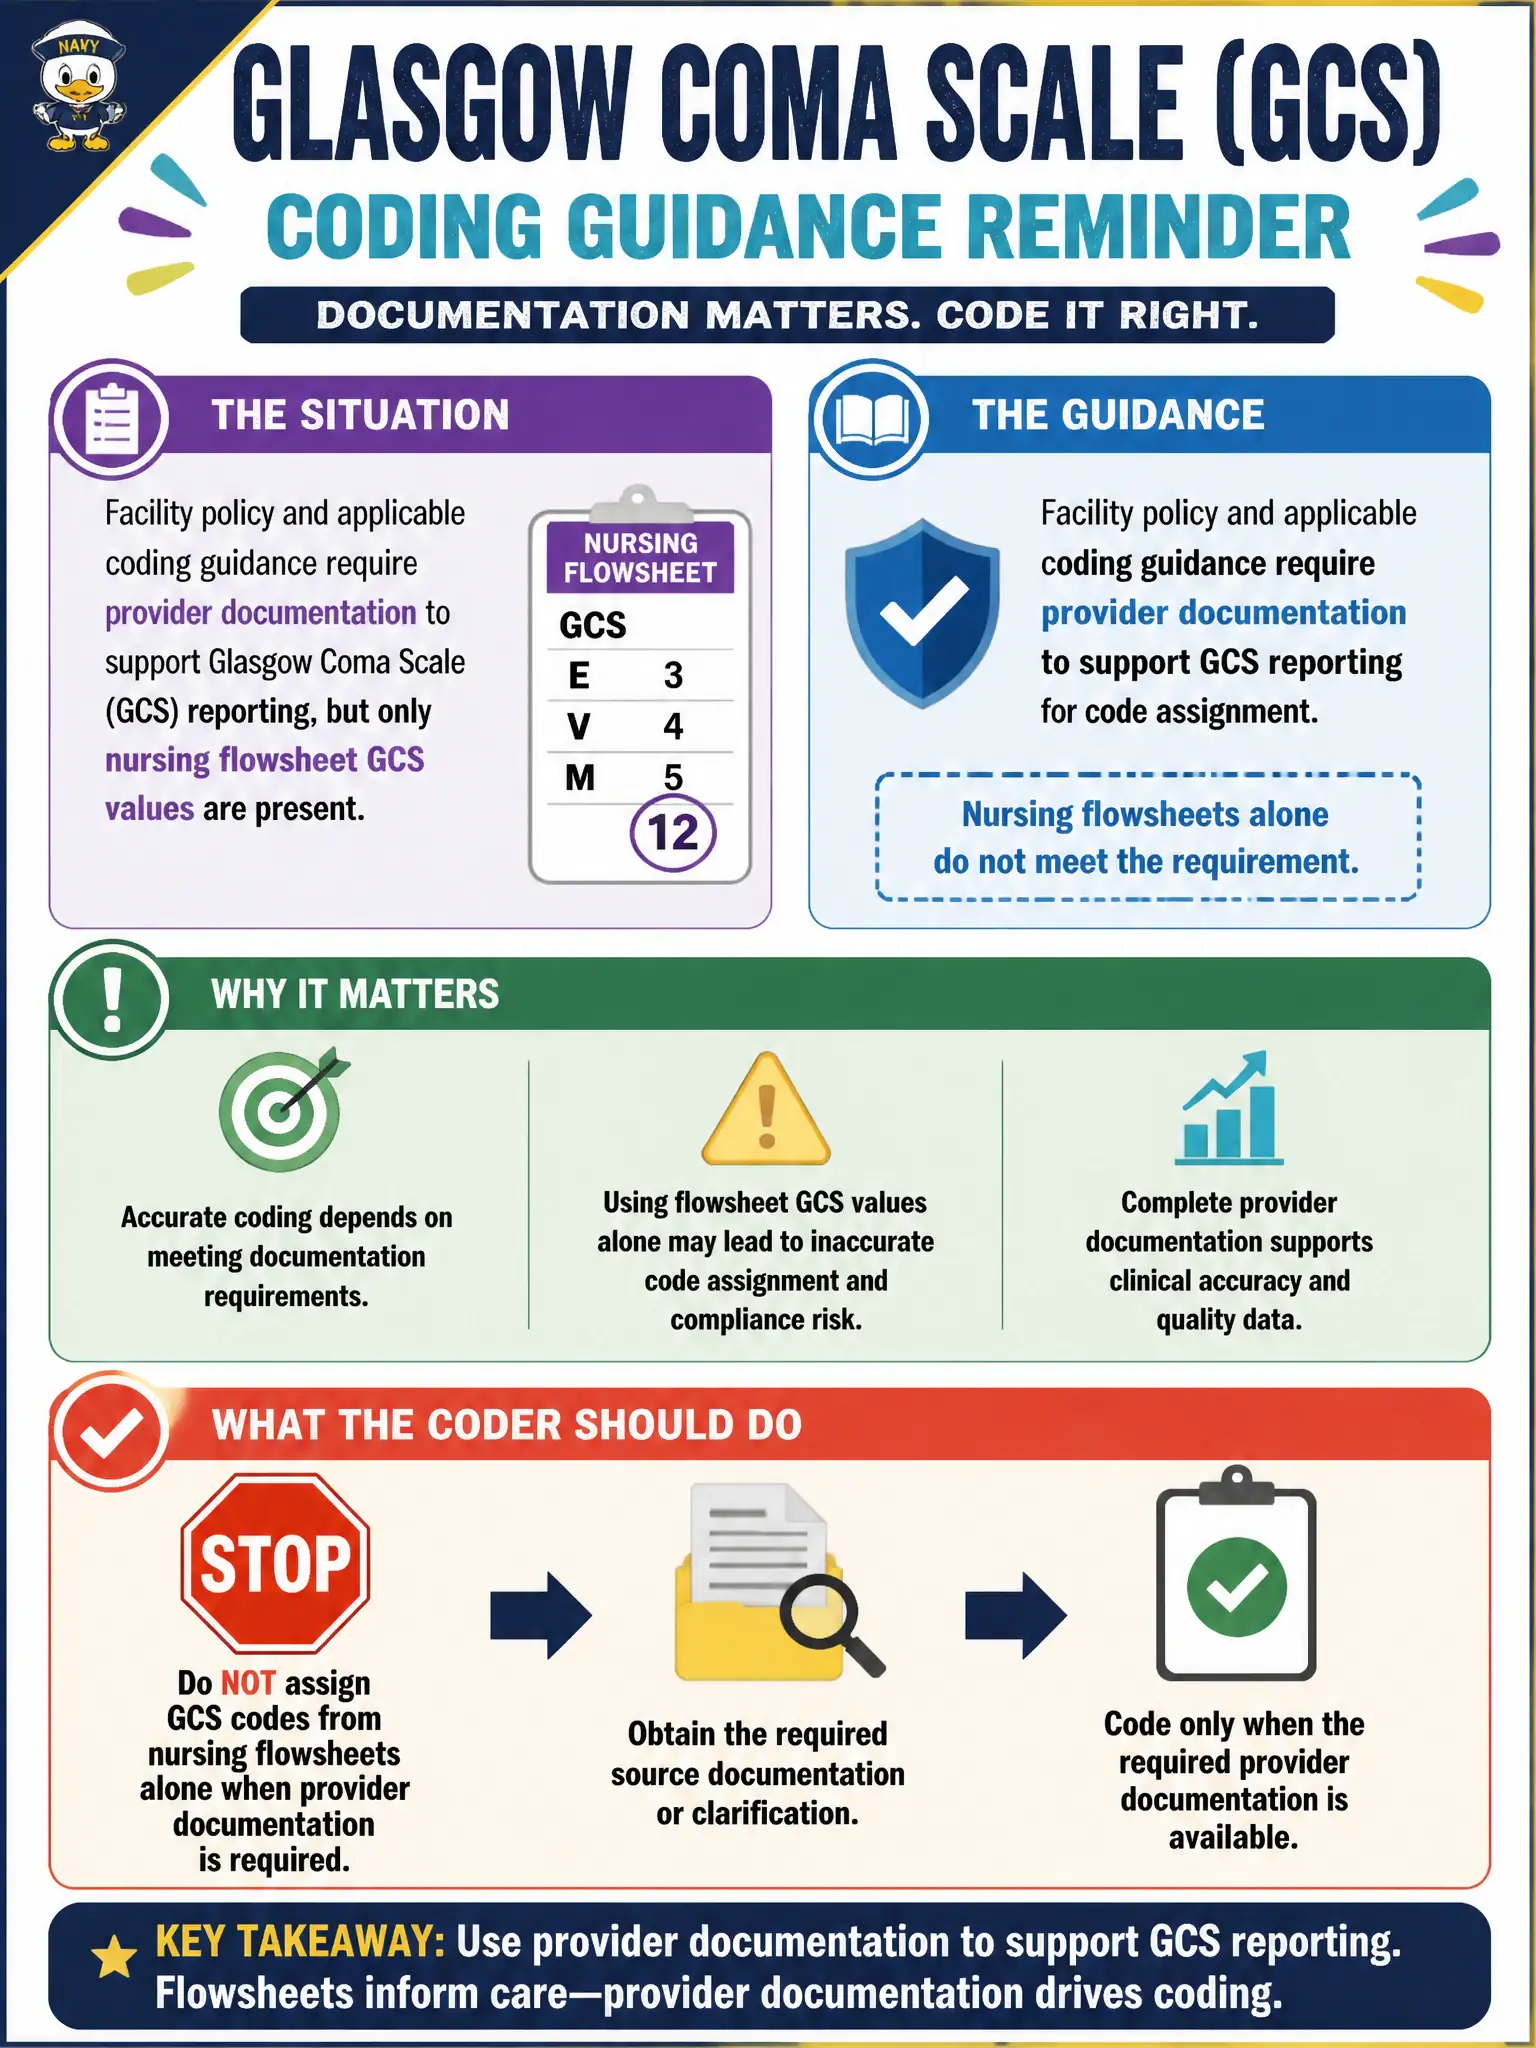
Facility policy and applicable coding guidance require provider documentation to support Glasgow Coma Scale reporting, but only nursing flowsheet GCS values are present. What should the coder do?
Select an answer to reveal the explanation.
Short Explanation
Some specialty scores are picky about who writes them down. If your rules say the provider must document GCS, a nursing flowsheet alone is not a free pass. Follow the required source — do not code from the wrong clipboard.
Full Explanation
Glasgow Coma Scale reporting can be subject to source rules: when facility policy and applicable coding guidance require provider documentation to support GCS codes, nursing flowsheet values alone are insufficient. The coder should not assign GCS codes from nursing flowsheets when a provider source is required; instead obtain the required documentation or clarification. Averaging nursing GCS scores invents a composite that no clinician documented as a reportable scale value. Coding from an ED triage board screenshot in an EHR header is not a substitute for authenticated provider GCS documentation under a provider-source rule. Converting each nursing GCS component into a separate principal diagnosis misuses scale components as stand-alone principal diagnoses and violates UHDDS principal diagnosis concepts. Exam caveat: Official Guidance and facility CDI/coding policy on who may document reportable scores can change—apply the rule set for the encounter rather than habit. Operational check: confirm whether provider documentation of GCS (total and/or components as required) exists for the relevant timeframe; if only nursing values are present under a provider-required policy, hold the GCS codes and escalate for proper documentation.