
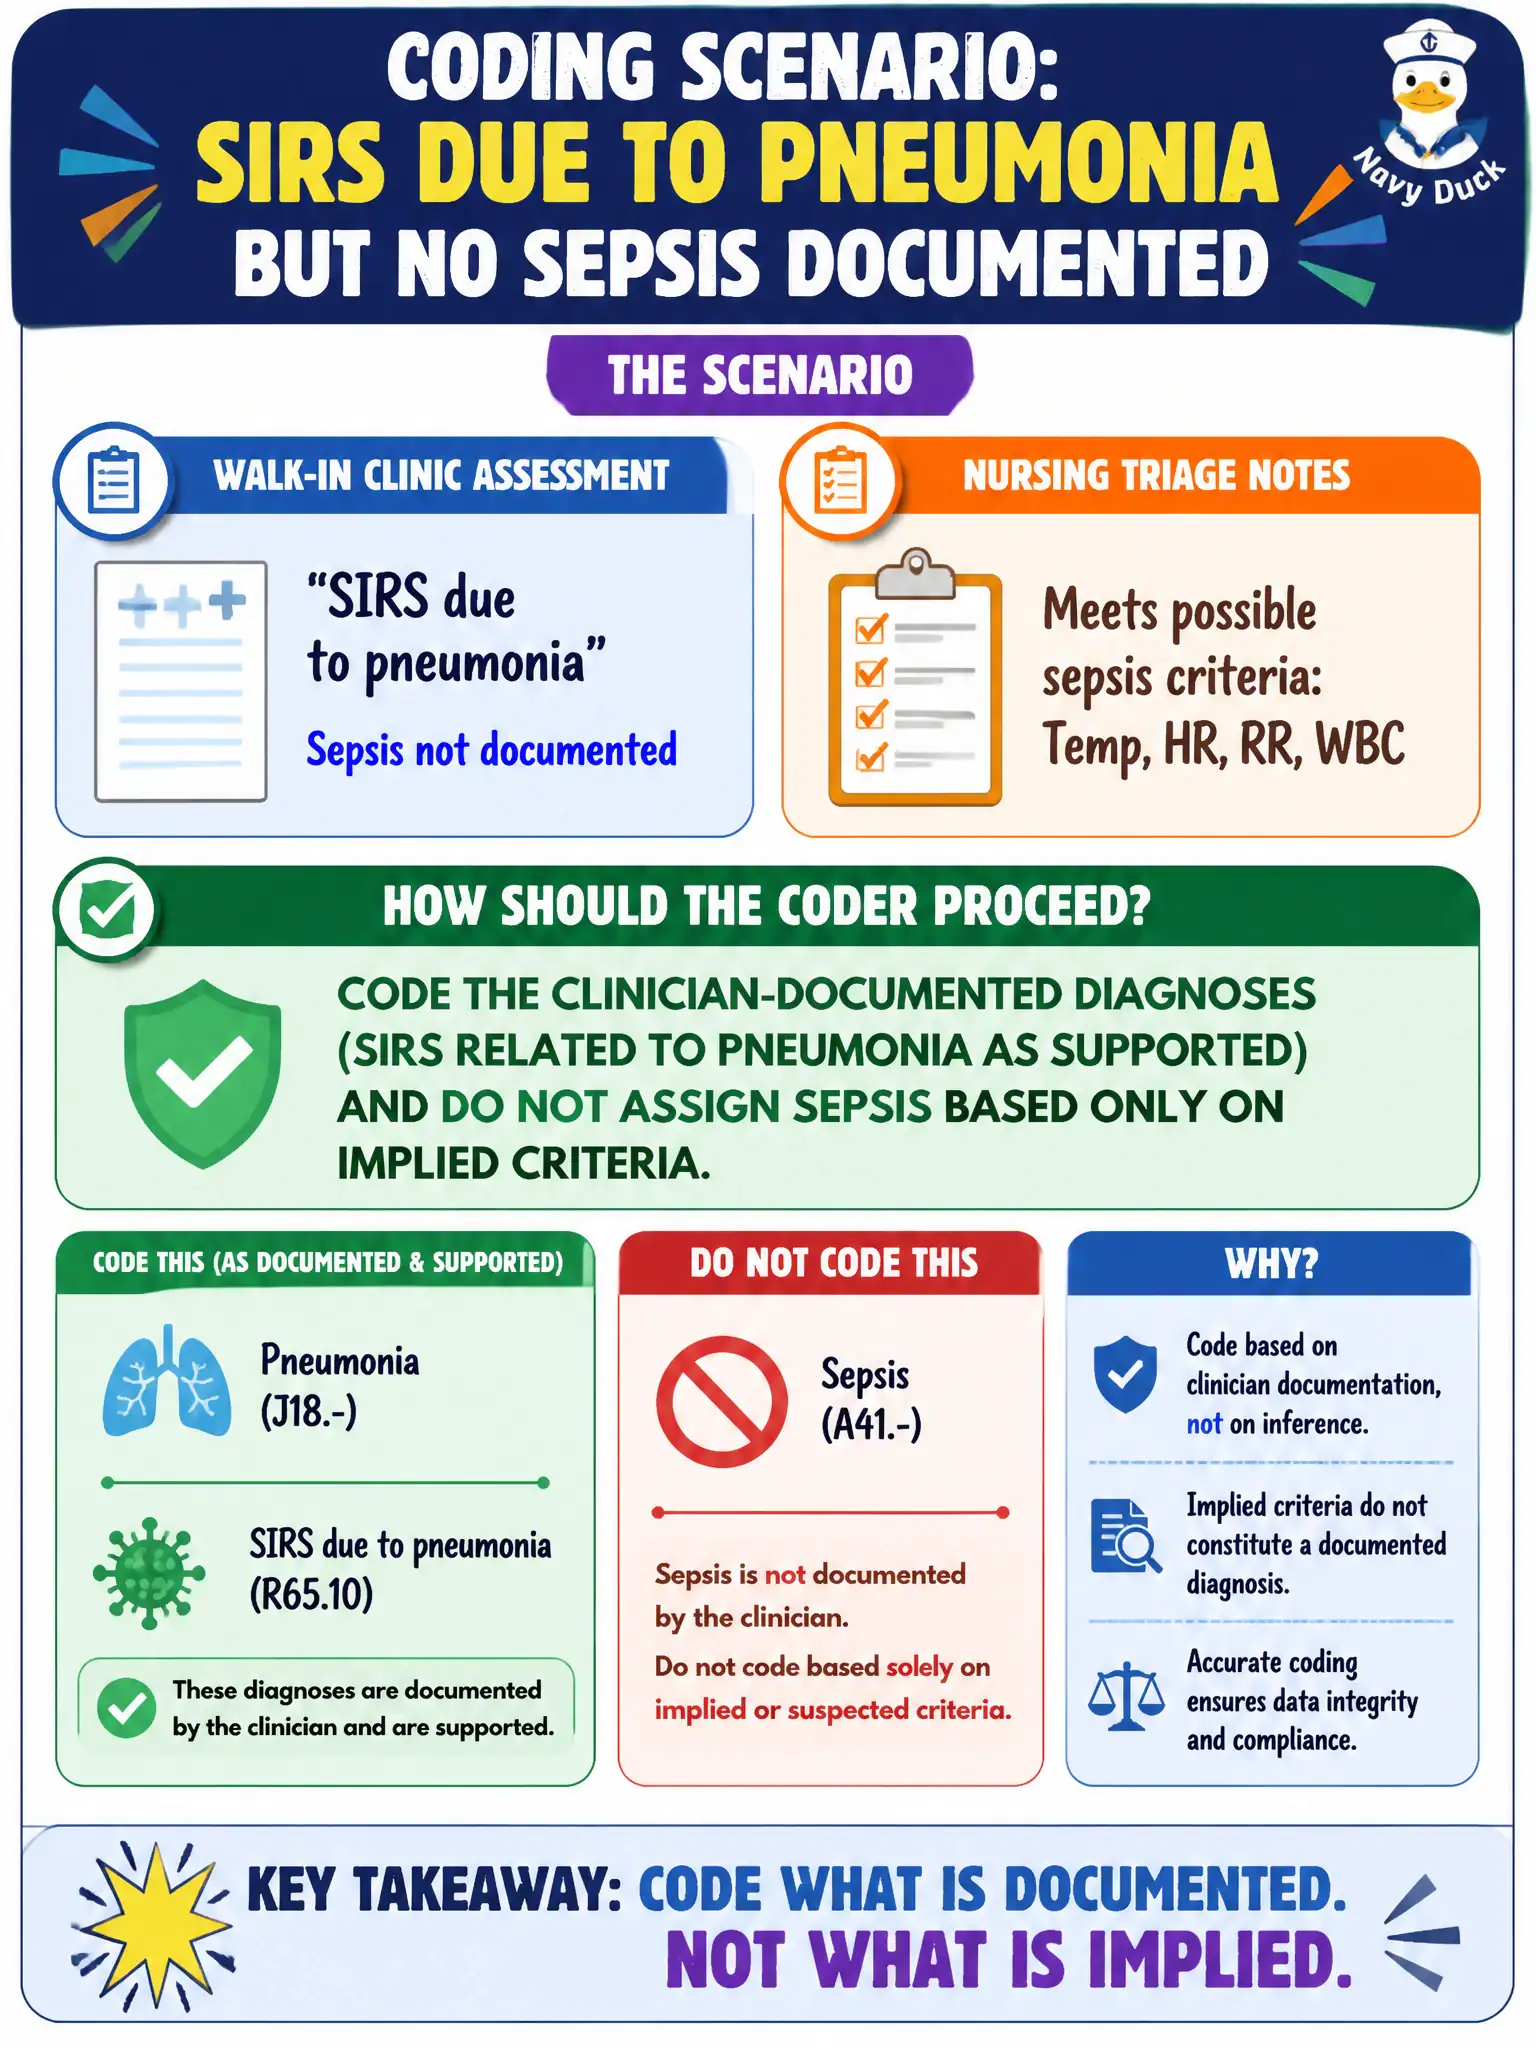
A walk-in clinic assessment states ‘SIRS due to pneumonia’ and does not document sepsis. Nursing triage notes mention possible sepsis criteria. How should the coder proceed?
Select an answer to reveal the explanation.
Short Explanation
Code what the clinician actually called it—not what the vitals might tempt you to assume. SIRS with pneumonia isn’t a free upgrade to sepsis without the provider saying so. If sepsis isn’t documented, don’t invent it.
Full Explanation
ICD-10-CM code assignment must reflect provider-documented diagnoses. When a walk-in clinic assessment states SIRS due to pneumonia and does not document sepsis, while nursing triage mentions possible sepsis criteria, code the clinician-documented diagnoses—SIRS related to pneumonia as supported—and do not assign sepsis based only on implied criteria. Automatically upcoding to sepsis whenever SIRS and an infection appear anywhere fails without provider documentation of sepsis. Coding only sepsis and omitting pneumonia because SIRS always equals sepsis fails both clinical and coding distinctions. Ignoring the physician assessment and coding from nursing triage impressions alone fails the provider-documentation rule. Exam caveat: a compliant query is appropriate when documentation is conflicting or incomplete, but criteria checklists alone do not establish sepsis. Operational check: follow the assessment language, report pneumonia and documented SIRS concepts as supported, withhold sepsis unless documented or clarified, and do not code from nursing impressions alone. In civic and community clinic workflows, document the chosen pathway in the coding rationale so auditors can see how the record supported specificity, sequencing, and instructional-note compliance on the professional claim.