
An adult inpatient needs a supine AP pelvis for hip pain and has a right total hip arthroplasty, with the pelvis centered to the table Bucky. All three AEC chambers are active and prior images cut off early and look light. Which AEC detector selection, anatomic alignment and exposure adjustment prevents premature cutoff and ensures uniform exposure?
Select an answer to reveal the explanation.
Short Explanation
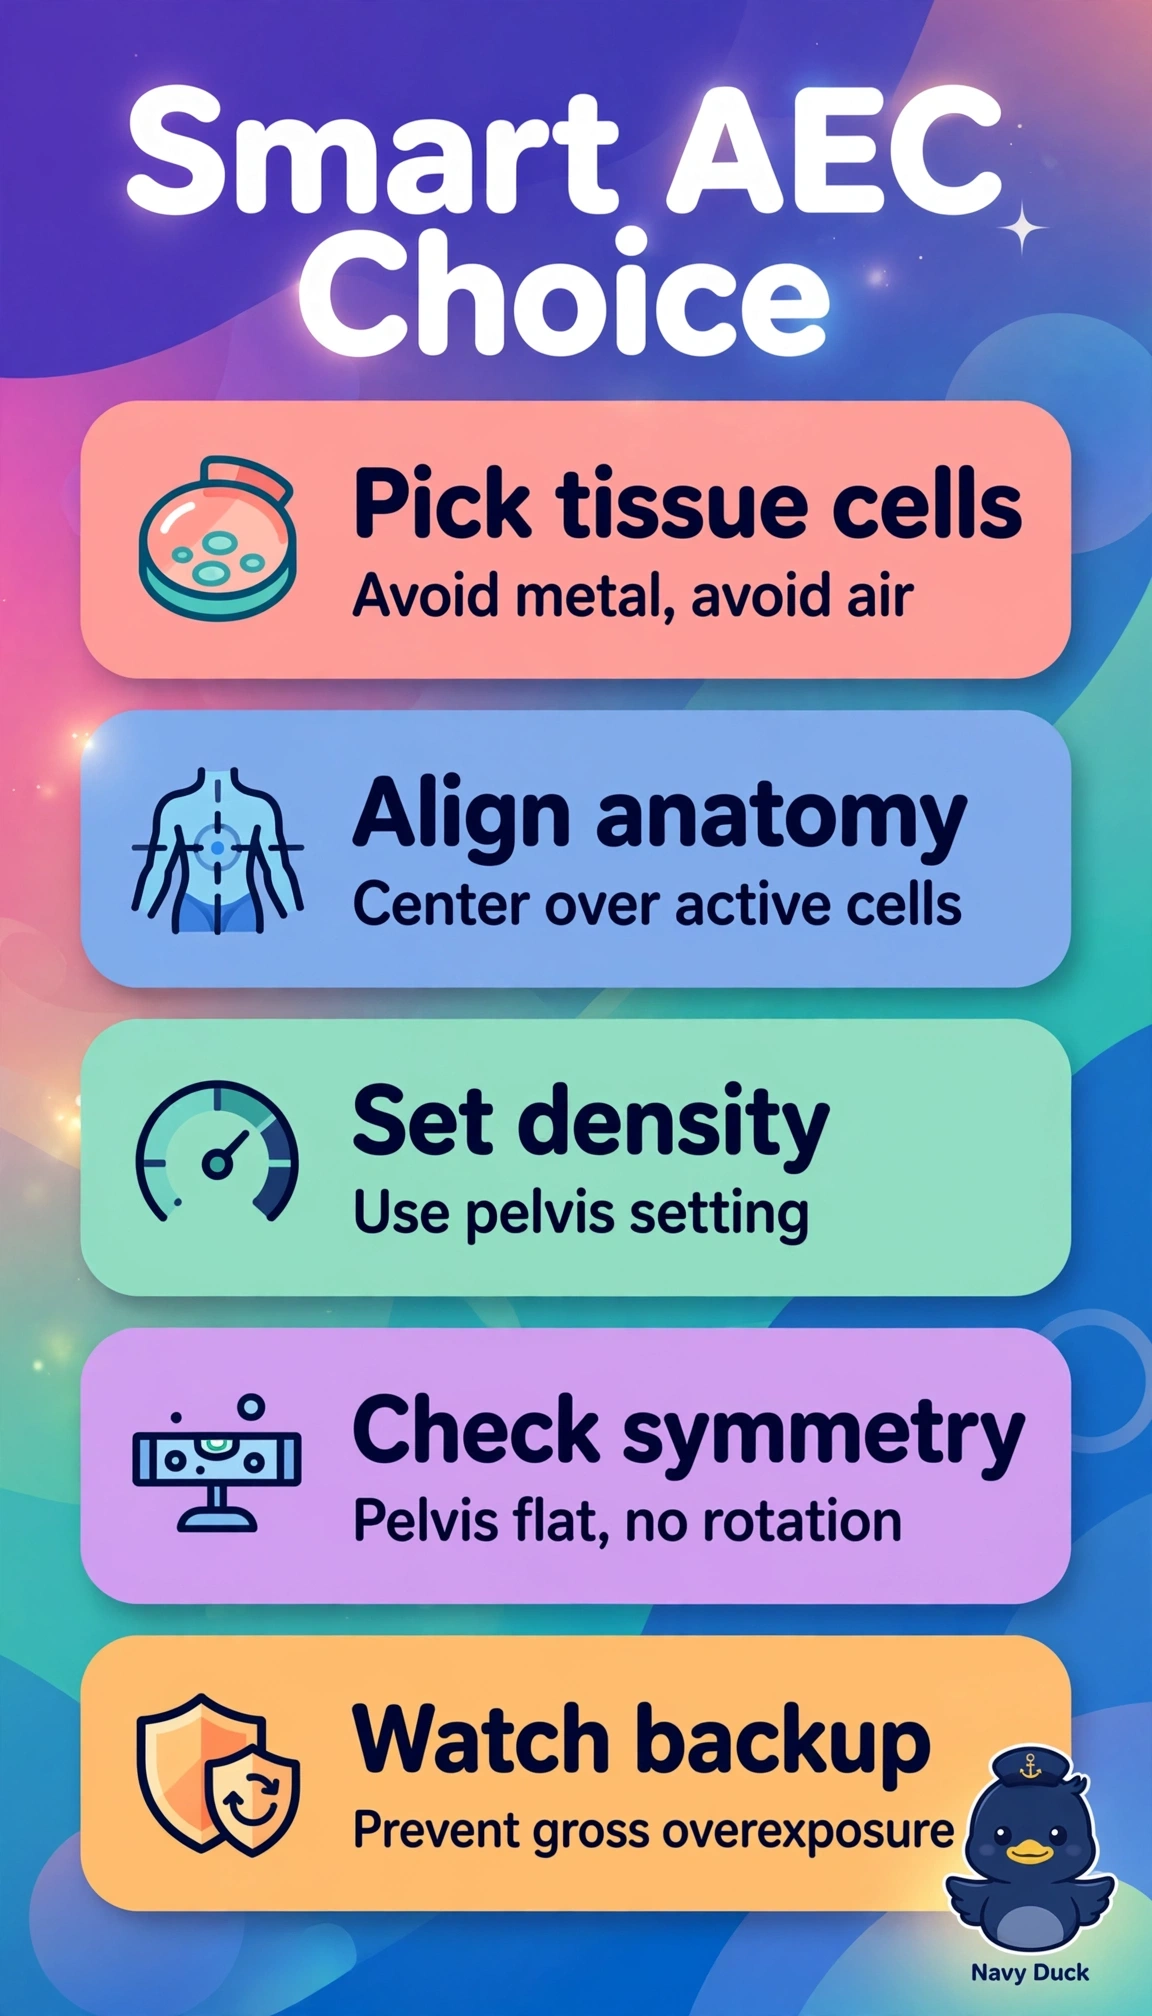
You're letting the sensor see tissue, not steel. Choosing covered detectors away from hardware stops early shutoff, and active chamber alignment keeps exposure honest across the pelvis.
Full Explanation
AEC terminates exposure when active ionization chambers receive the preset charge, so any chamber under metal or air shuts off early or late and mis-exposes the image; selecting only detectors fully covered by soft tissue of interest away from arthroplasty metal, aligning that anatomy precisely over the active cells, and using the normal pelvic density setting produces consistent receptor exposure. That prevents the prosthesis from fooling the system into a light image. Keeping all chambers active over the prosthesis lets the dense metal dominate and cut exposure short, and lowering density further lightens the image. Activating only the chamber behind the prosthesis guarantees premature cutoff because metal attenuates the beam, and tilting the pelvis distorts symmetry and introduces rotation. Deactivating all chambers and guessing a low fixed mAs at the table edge abandons AEC control and risks severe underexposure without backup-time safety. Exam caveat: chamber choice follows tissue coverage, not habit — always confirm which cells are active and covered. Practical check: position symmetrically, verify active lights, ensure no metal or air over them, and recenter if needed.