
An urgent-care adult with high BMI presents for follow-up of a tibial shaft fracture in a thick plaster cast, with marked soft-tissue swelling. The routine lower-leg technique yields a noisy, light image with poor cortical detail. The ordering provider wants to avoid repeat CT. Which technique adaptation compensates for cast and habitus while preserving contrast for fracture assessment?
Select an answer to reveal the explanation.
Short Explanation
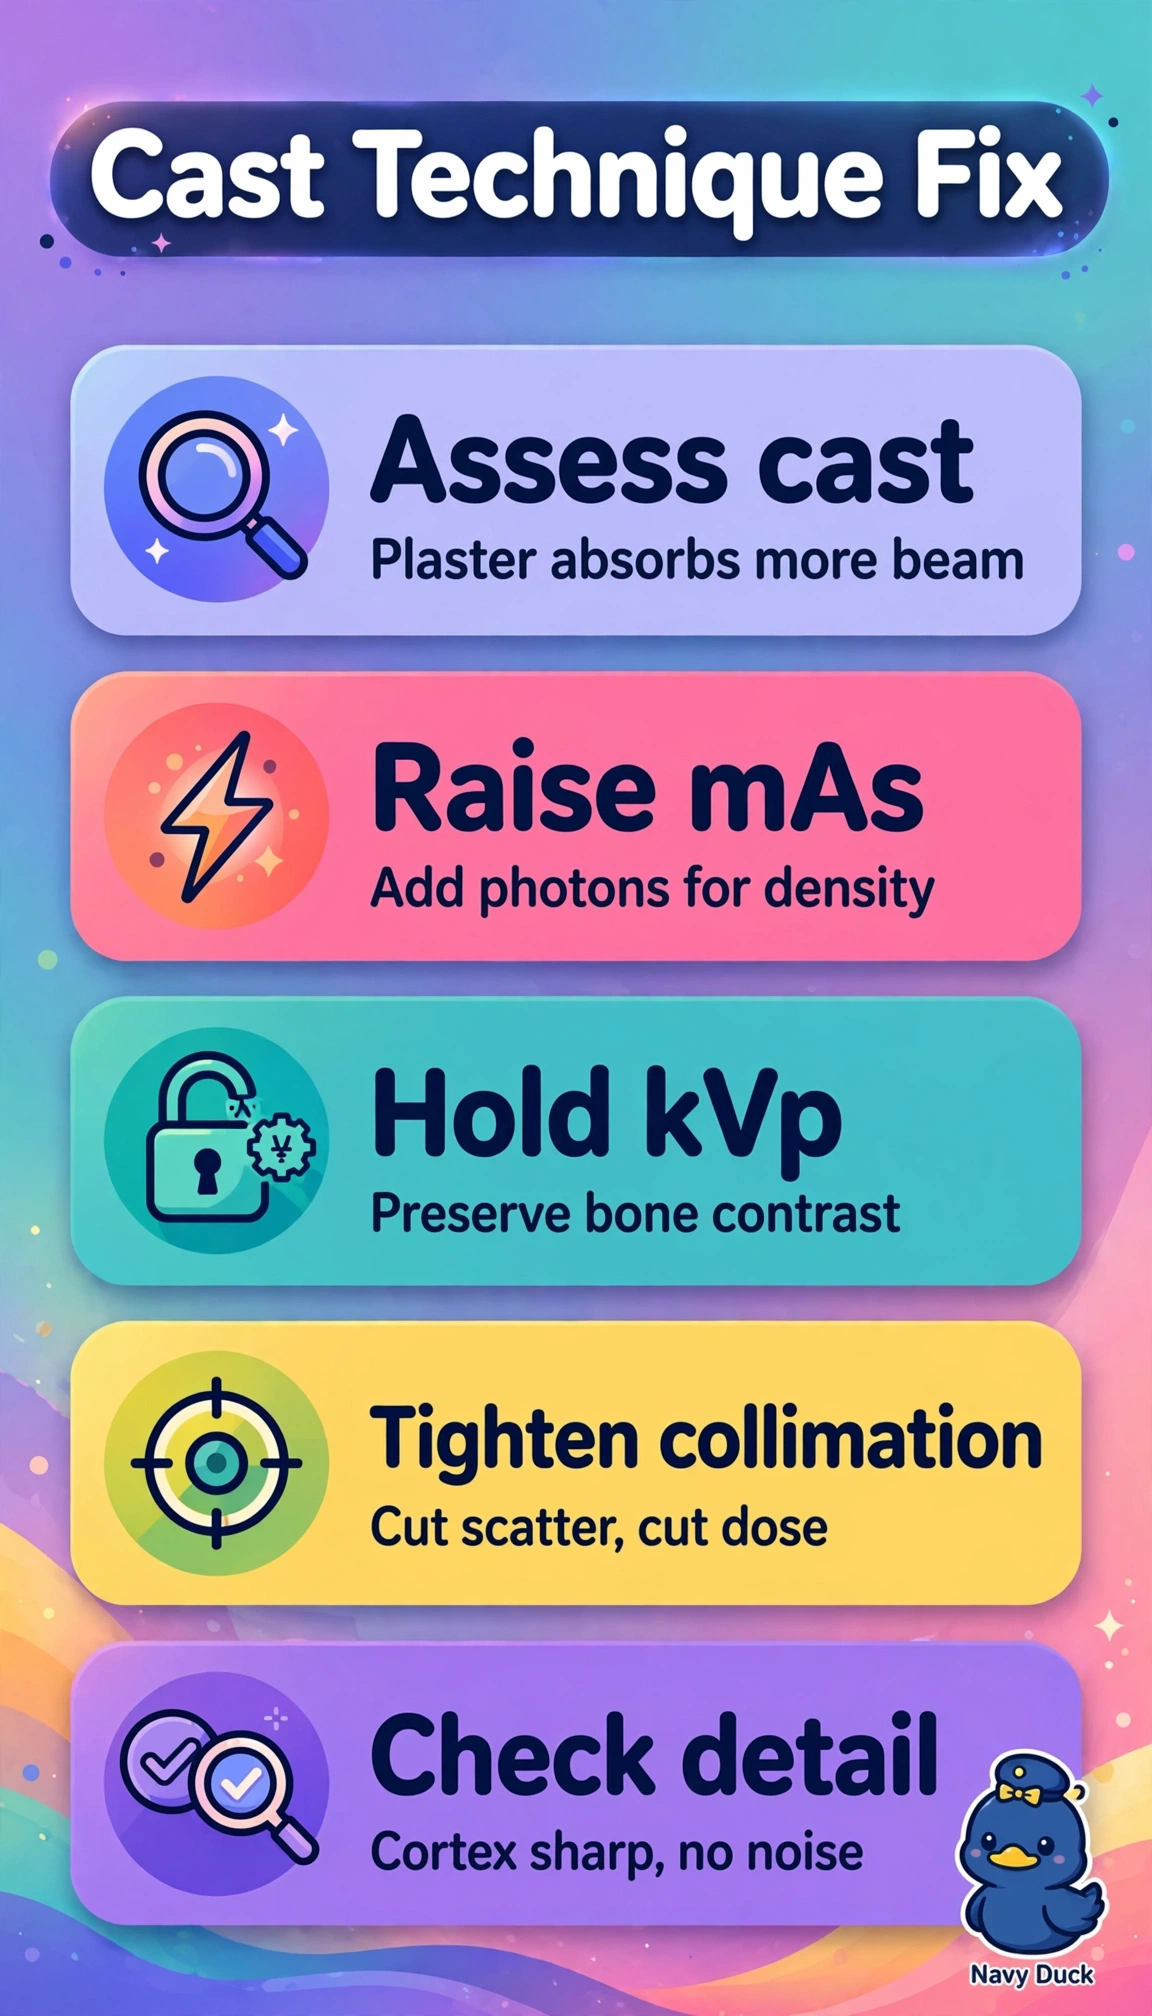
You need more photons to punch through plaster, not just hotter photons. Extra mAs restores density while steady kVp keeps bone contrast, so penetration balance saves this follow-up.
Full Explanation
Plaster casts and edematous soft tissue plus larger body habitus attenuate the beam and starve the receptor, producing quantum noise and low density; increasing mAs provides the needed quantity of photons to penetrate without markedly changing the contrast scale, while holding kVp near the routine level preserves differential attenuation between bone and soft tissue for fracture line visibility and tight collimation limits scatter and dose. That balance restores exposure while maintaining diagnostic contrast. Sharply decreasing mAs while markedly raising kVp and opening the field further starves the receptor in one direction and then washes out contrast and adds scatter in the other. Holding mAs fixed while substantially lowering kVp leaves the beam too weak to penetrate plaster, worsening noise and risking repeats. Increasing kVp alone with lower mAs and a wide field reduces contrast, increases scatter fog, and adds unnecessary tissue to the image. Exam caveat: fiberglass needs a smaller bump than bulky plaster, and swollen or bariatric parts need exposure increase not kVp escape. Practical check: increase in steps, collimate to the tibia, and verify cortical detail and joint inclusion before repeating.