
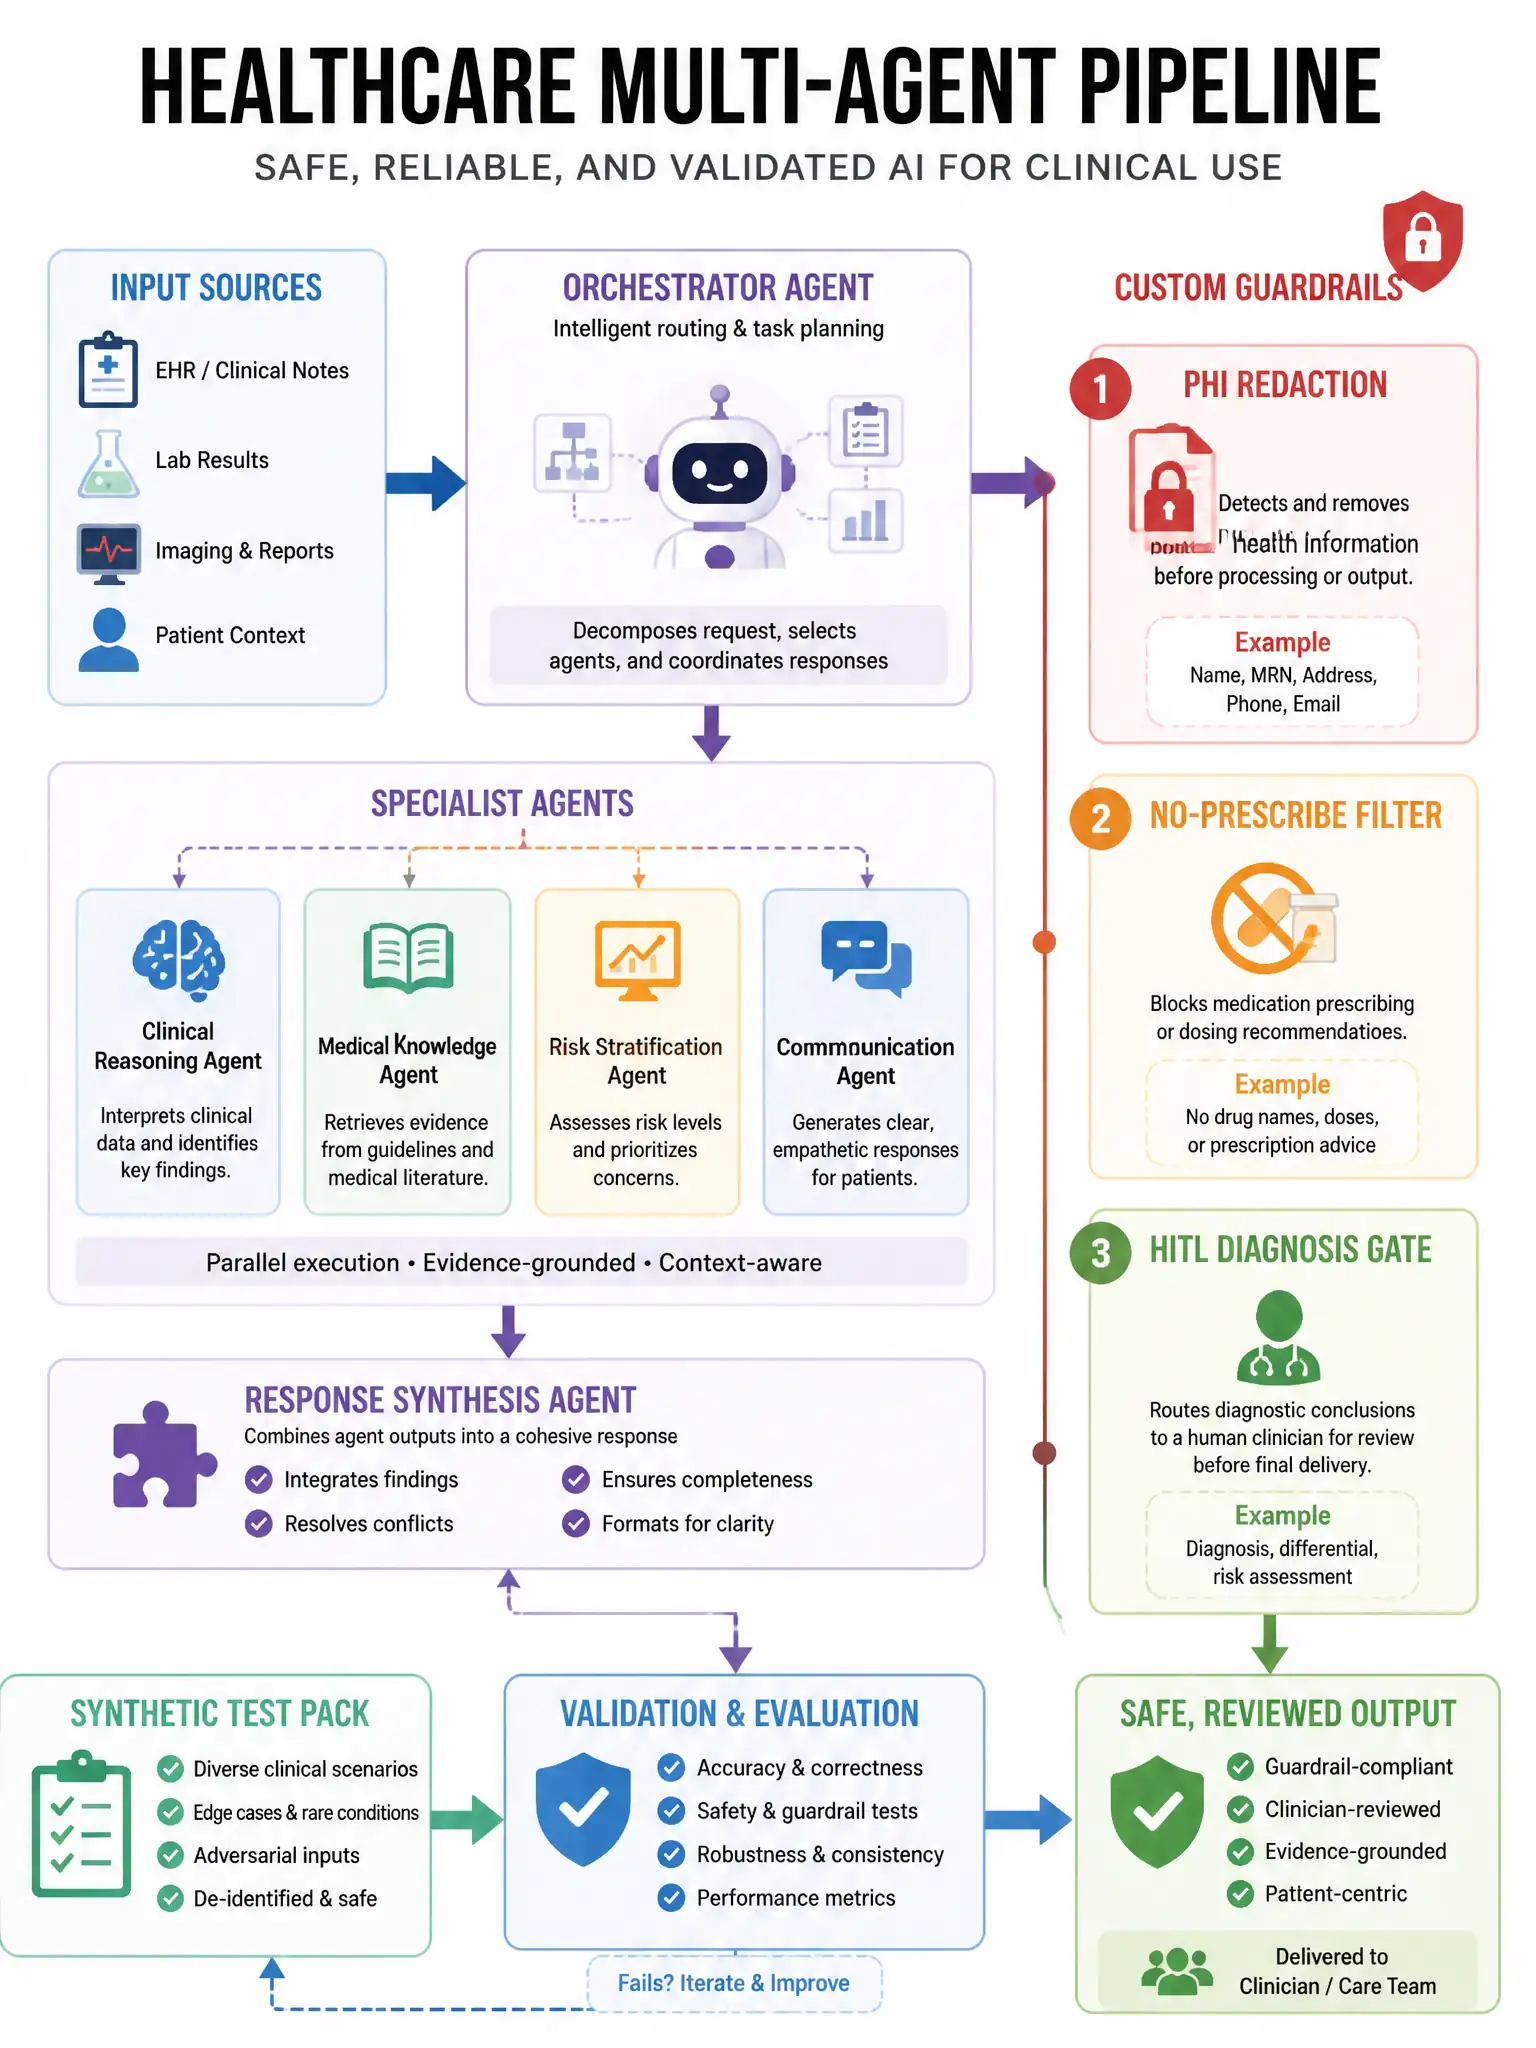
A hospital is piloting multi-agent triage helpers that draft clinical summaries. Beyond generic content safety, policies forbid diagnosing rare conditions without clinician review, forbid prescribing language, and require PHI redaction before any external tool call. How should you implement these requirements?
Select an answer to reveal the explanation.
Short Explanation
You need custom domain guardrails, not just generic filters. Force human review for diagnosis drafts, scrub PHI before external calls, and validate with synthetic clinical tests. Wikis, temperature tweaks, and dropping retrieval won't enforce policy.
Full Explanation
The secure/govern domain of AI-500 includes designing custom guardrails for domain-specific constraints and testing them with synthetic data. Healthcare is a canonical example: policy is richer than hate/violence categories. Implement classifiers or rule engines for forbidden action verbs such as prescribing or dose changes, route diagnosis-class drafts to human-in-the-loop queues, and apply deterministic PHI detection before MCP or HTTP tools leave the trust boundary. Version guardrail configs alongside agent definitions. The wiki-and-training approach is process-only. Increasing model temperature confuses sampling with safety. Removing retrieval entirely reduces capability without encoding the actual clinical policies. Measure false positives so clinicians still get useful drafts, and log guardrail interventions for audit and continuous improvement.