
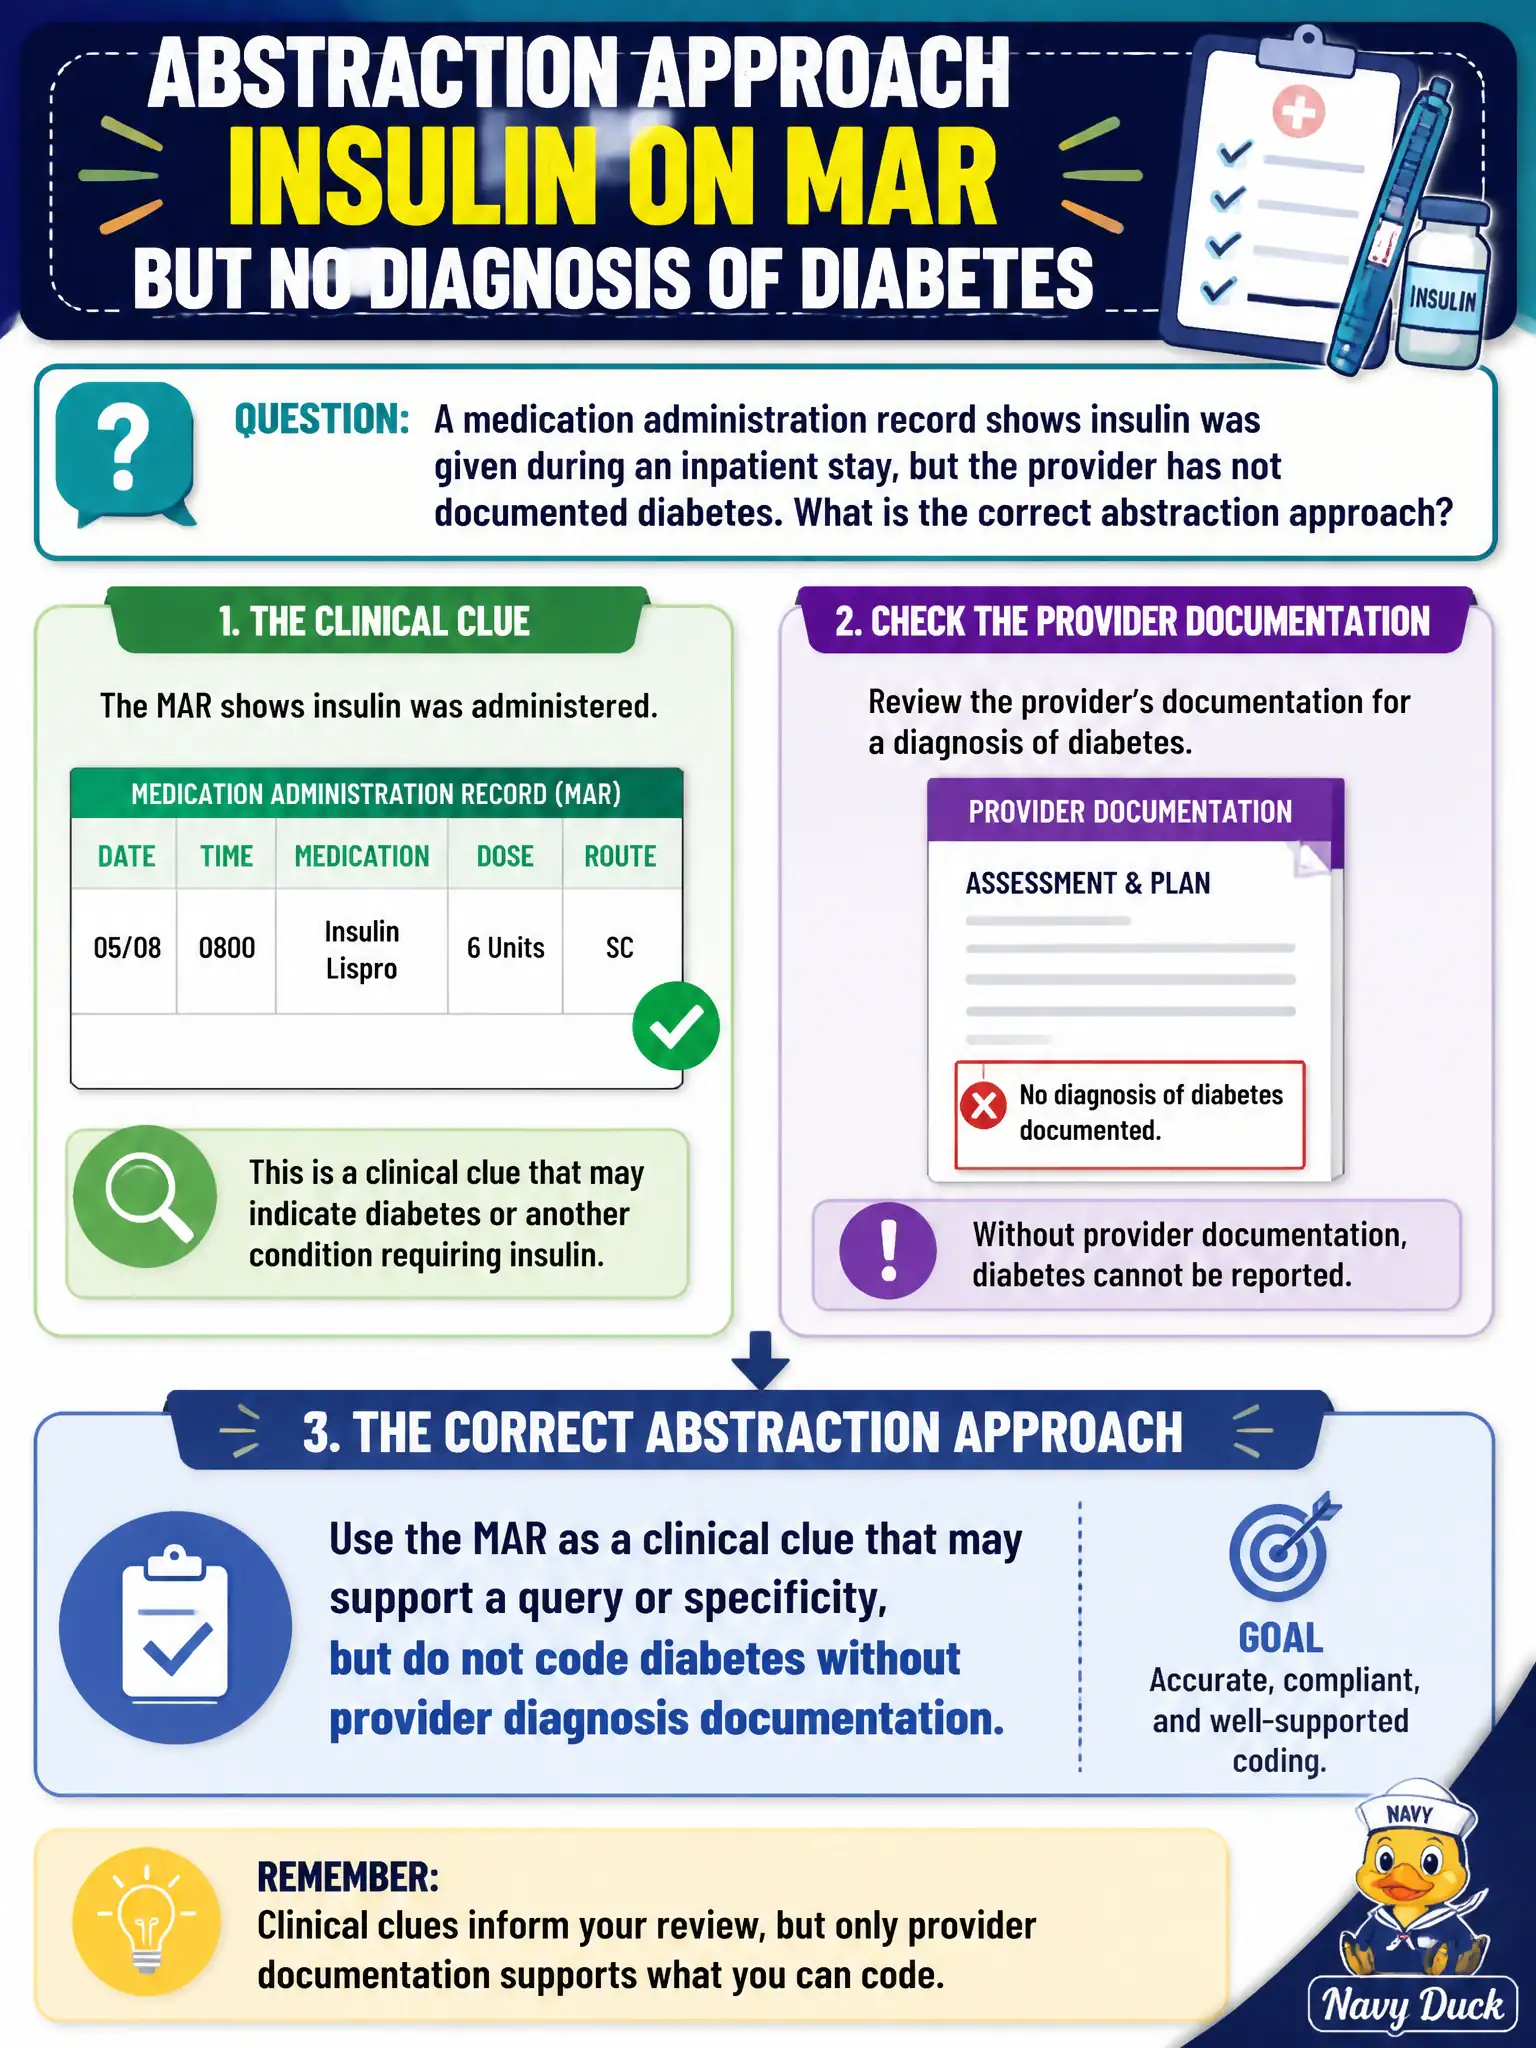
A medication administration record shows insulin was given during an inpatient stay, but the provider has not documented diabetes. What is the correct abstraction approach?
Select an answer to reveal the explanation.
Short Explanation
The MAR is a helpful breadcrumb—insulin on the list makes you wonder about diabetes—but breadcrumbs aren’t the diagnosis. You still need the provider to say it (or answer a solid query). Meds support; they don’t replace the doc’s words.
Full Explanation
When a medication administration record shows insulin was given during an inpatient stay but the provider has not documented diabetes, the correct abstraction approach is to treat the MAR as a clinical clue that may support a query or specificity—not to code diabetes without provider diagnosis documentation. Public hospital coding ethics require provider-authenticated diagnoses for reportable conditions. Coding diabetes mellitus from the MAR alone fails because medication administration does not independently establish the diagnosis for coding. Deleting all endocrine-related codes because medications cannot be reviewed fails; ancillary sources may appropriately support queries and specificity when a diagnosis is documented. Automatically reporting an MCC for diabetes whenever any insulin appears fails as payment-driven coding without documentation. Exam caveat: medications can cue queries; they do not replace provider diagnosis documentation for coding diabetes. Operational check: if insulin appears without a diabetes diagnosis on a civic inpatient chart, search for clinical indicators, query when warranted, and withhold diabetes coding until documented. Never manufacture MCC-level endocrine codes from the MAR alone during concurrent or retrospective review.