
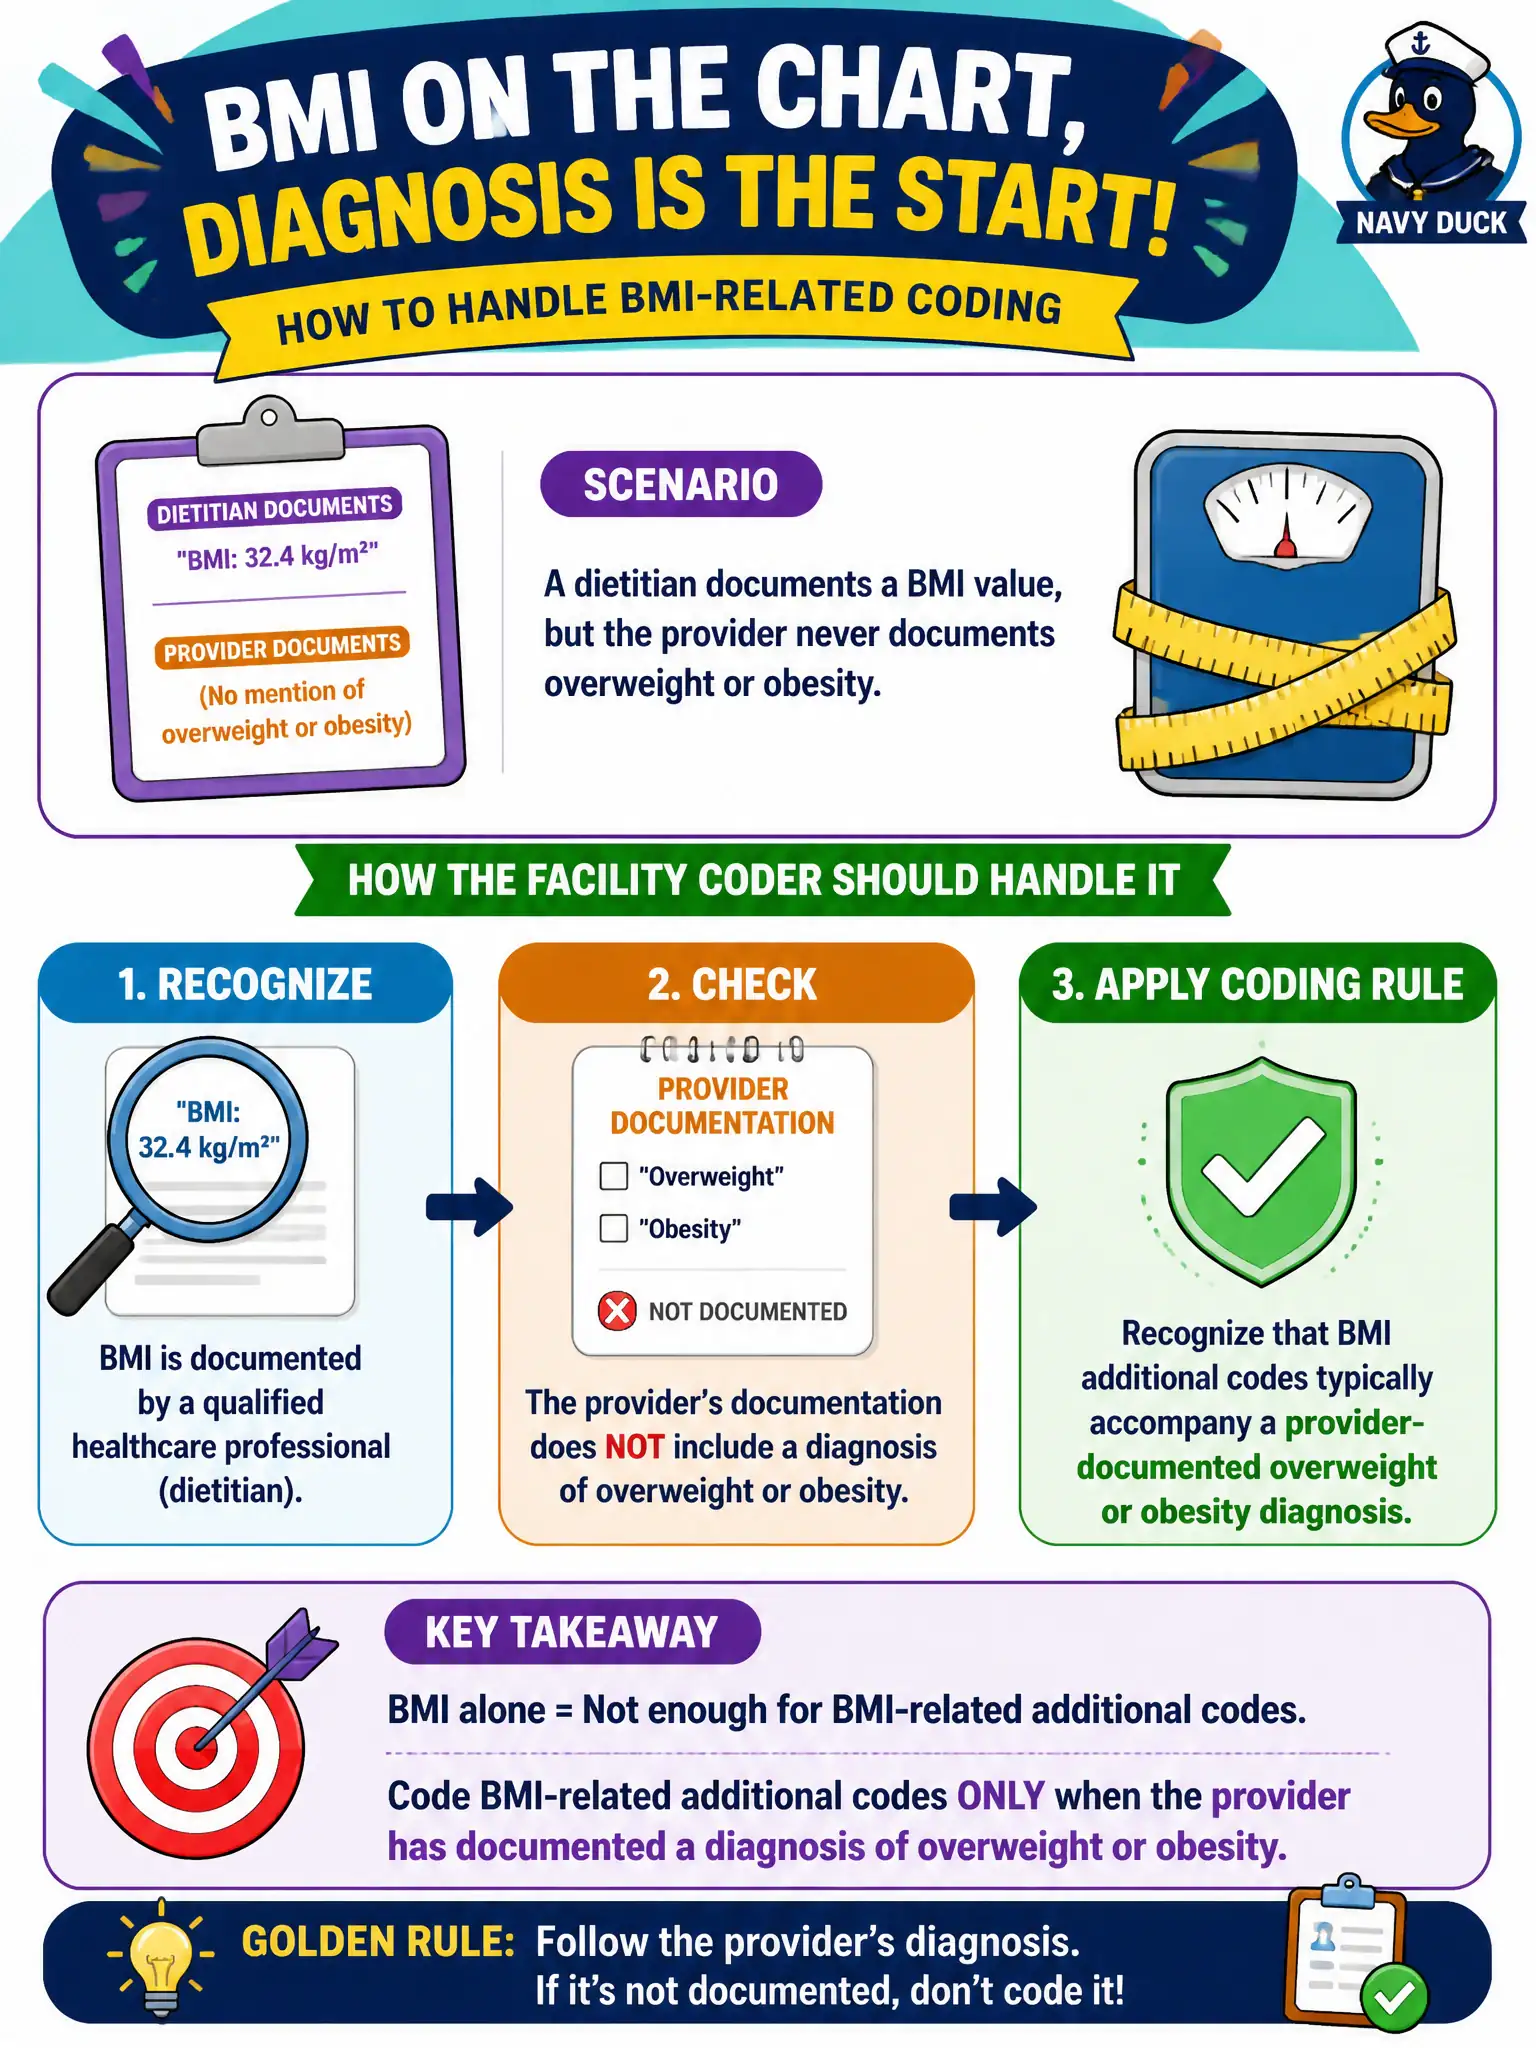
A dietitian documents a BMI value, but the provider never documents overweight or obesity. How should the facility coder handle BMI-related coding?
Select an answer to reveal the explanation.
Short Explanation
BMI is the measuring tape; obesity is the diagnosis. Tape measurements from nutrition are useful, but you usually still need the provider to document overweight or obesity before BMI rides along as an additional code.
Full Explanation
When a dietitian documents a BMI value but the provider never documents overweight or obesity, the facility coder should recognize that BMI additional codes typically accompany a provider-documented overweight or obesity diagnosis. Civic coding follows Official Guidelines linking BMI codes to those diagnoses rather than inventing obesity from nutrition measurements alone. Assigning obesity and BMI codes from the dietitian BMI alone fails without the associated provider diagnosis. Converting the BMI into an obesity class code without a provider diagnosis fails the same requirement. Deleting the BMI from the abstract because dietitian notes are never used in coding fails when BMI may be appropriately reported with a supported overweight/obesity diagnosis—nutrition notes are not categorically unusable. Exam caveat: BMI codes are additional and typically need provider overweight/obesity documentation. Operational check: if BMI is documented without obesity diagnosis on a municipal chart, query when clinical indicators support overweight/obesity; code BMI with the authenticated diagnosis; do not create obesity from BMI alone or discard usable BMI when the diagnosis exists. In municipal and county facility practice, record the rationale for the chosen coding path and the rejected alternatives in the abstract notes so auditors and future coders understand the clinical and compliance basis. Re-check the decision if new authenticated documentation arrives before final bill drop, and escalate persistent documentation gaps to CDI or compliance rather than normalizing unsupported shortcuts that would distort civic claims, quality metrics, or case-mix reporting.