
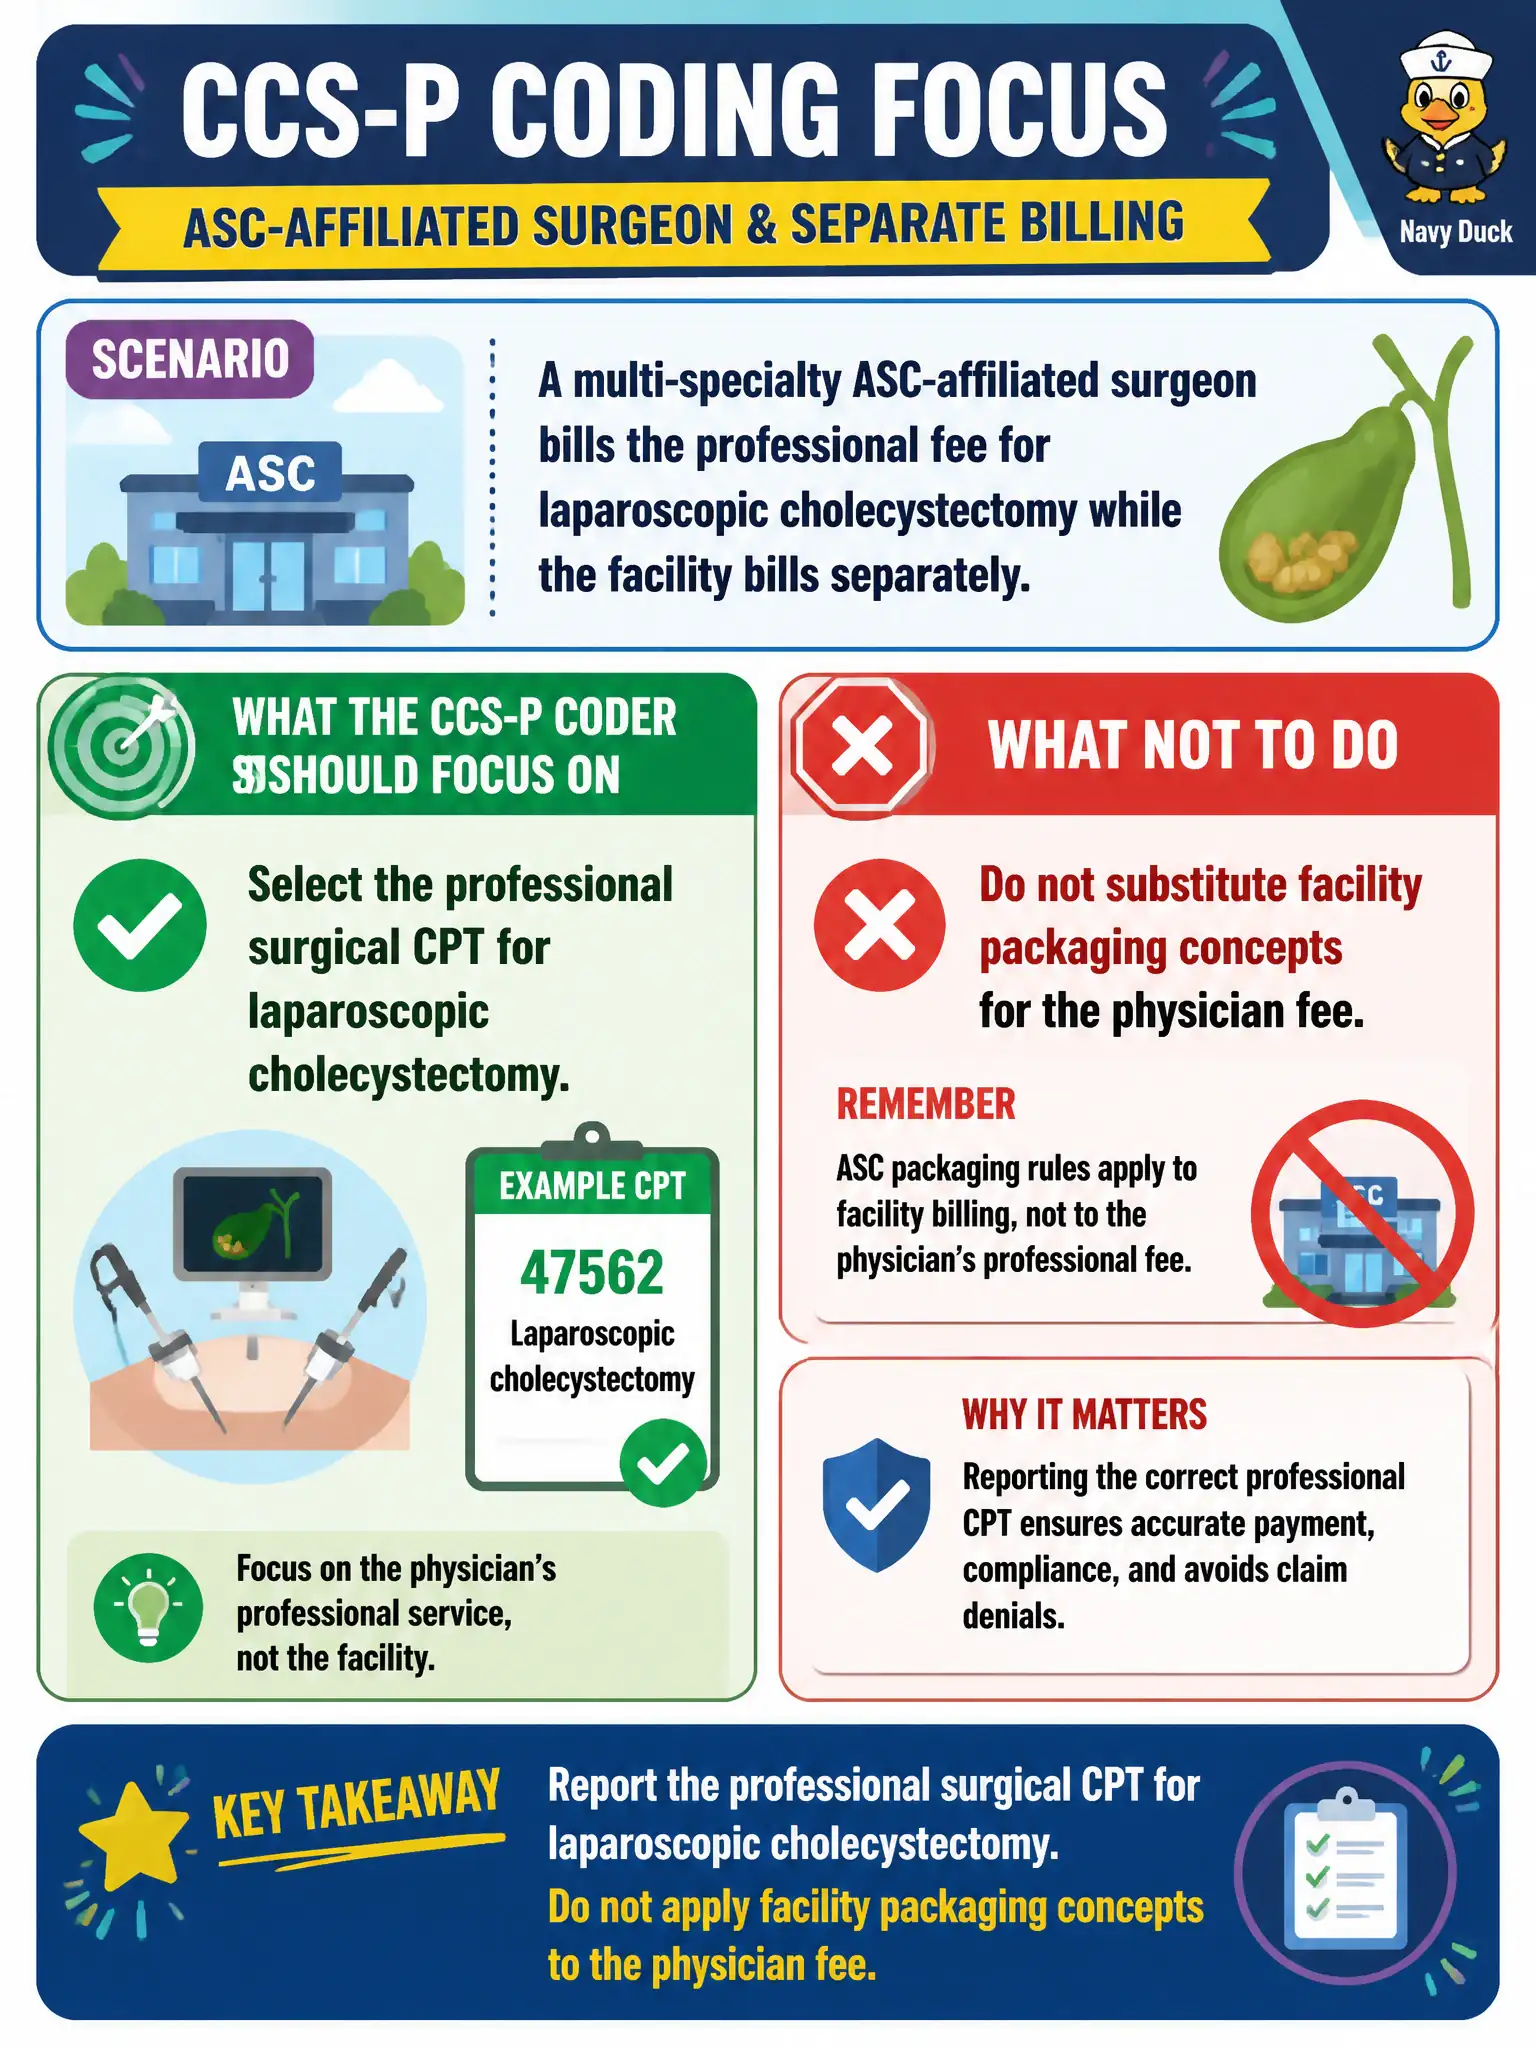
A multi-specialty ASC-affiliated surgeon bills the professional fee for laparoscopic cholecystectomy while the facility bills separately. What should the CCS-P coder focus on?
Select an answer to reveal the explanation.
Short Explanation
The surgeon’s paycheck story is the professional CPT for the lap chole; the building’s bill is a different story. Don’t paste facility APC logic onto the physician claim or pretend surgeons don’t code procedures in an ASC.
Full Explanation
When a multi-specialty ASC-affiliated surgeon bills the professional fee for laparoscopic cholecystectomy while the facility bills separately, the CCS-P coder focuses on the professional surgical CPT for that laparoscopic cholecystectomy and does not substitute facility packaging concepts on the physician claim. Clear professional-versus-facility separation protects community surgical payment integrity and prevents double-concept confusion on Part B claims.
Assigning facility APC or packaging logic on the professional claim instead of surgical CPT misapplies outpatient facility payment methodology to physician billing. Omitting surgical CPT because ASC cases are never reported on physician claims is false—surgeons still report professional surgical codes. Reporting only anesthesia time units for the surgeon’s professional service confuses anesthesia billing with the surgeon’s operative CPT.
Exam caveat: assistant, co-surgery, and global package modifiers may still apply on the professional claim independent of the ASC facility bill. Operational check: select the laparoscopic cholecystectomy professional CPT, confirm place of service for ASC, coordinate modifiers with the operative note, and leave APC packaging on the facility claim.