
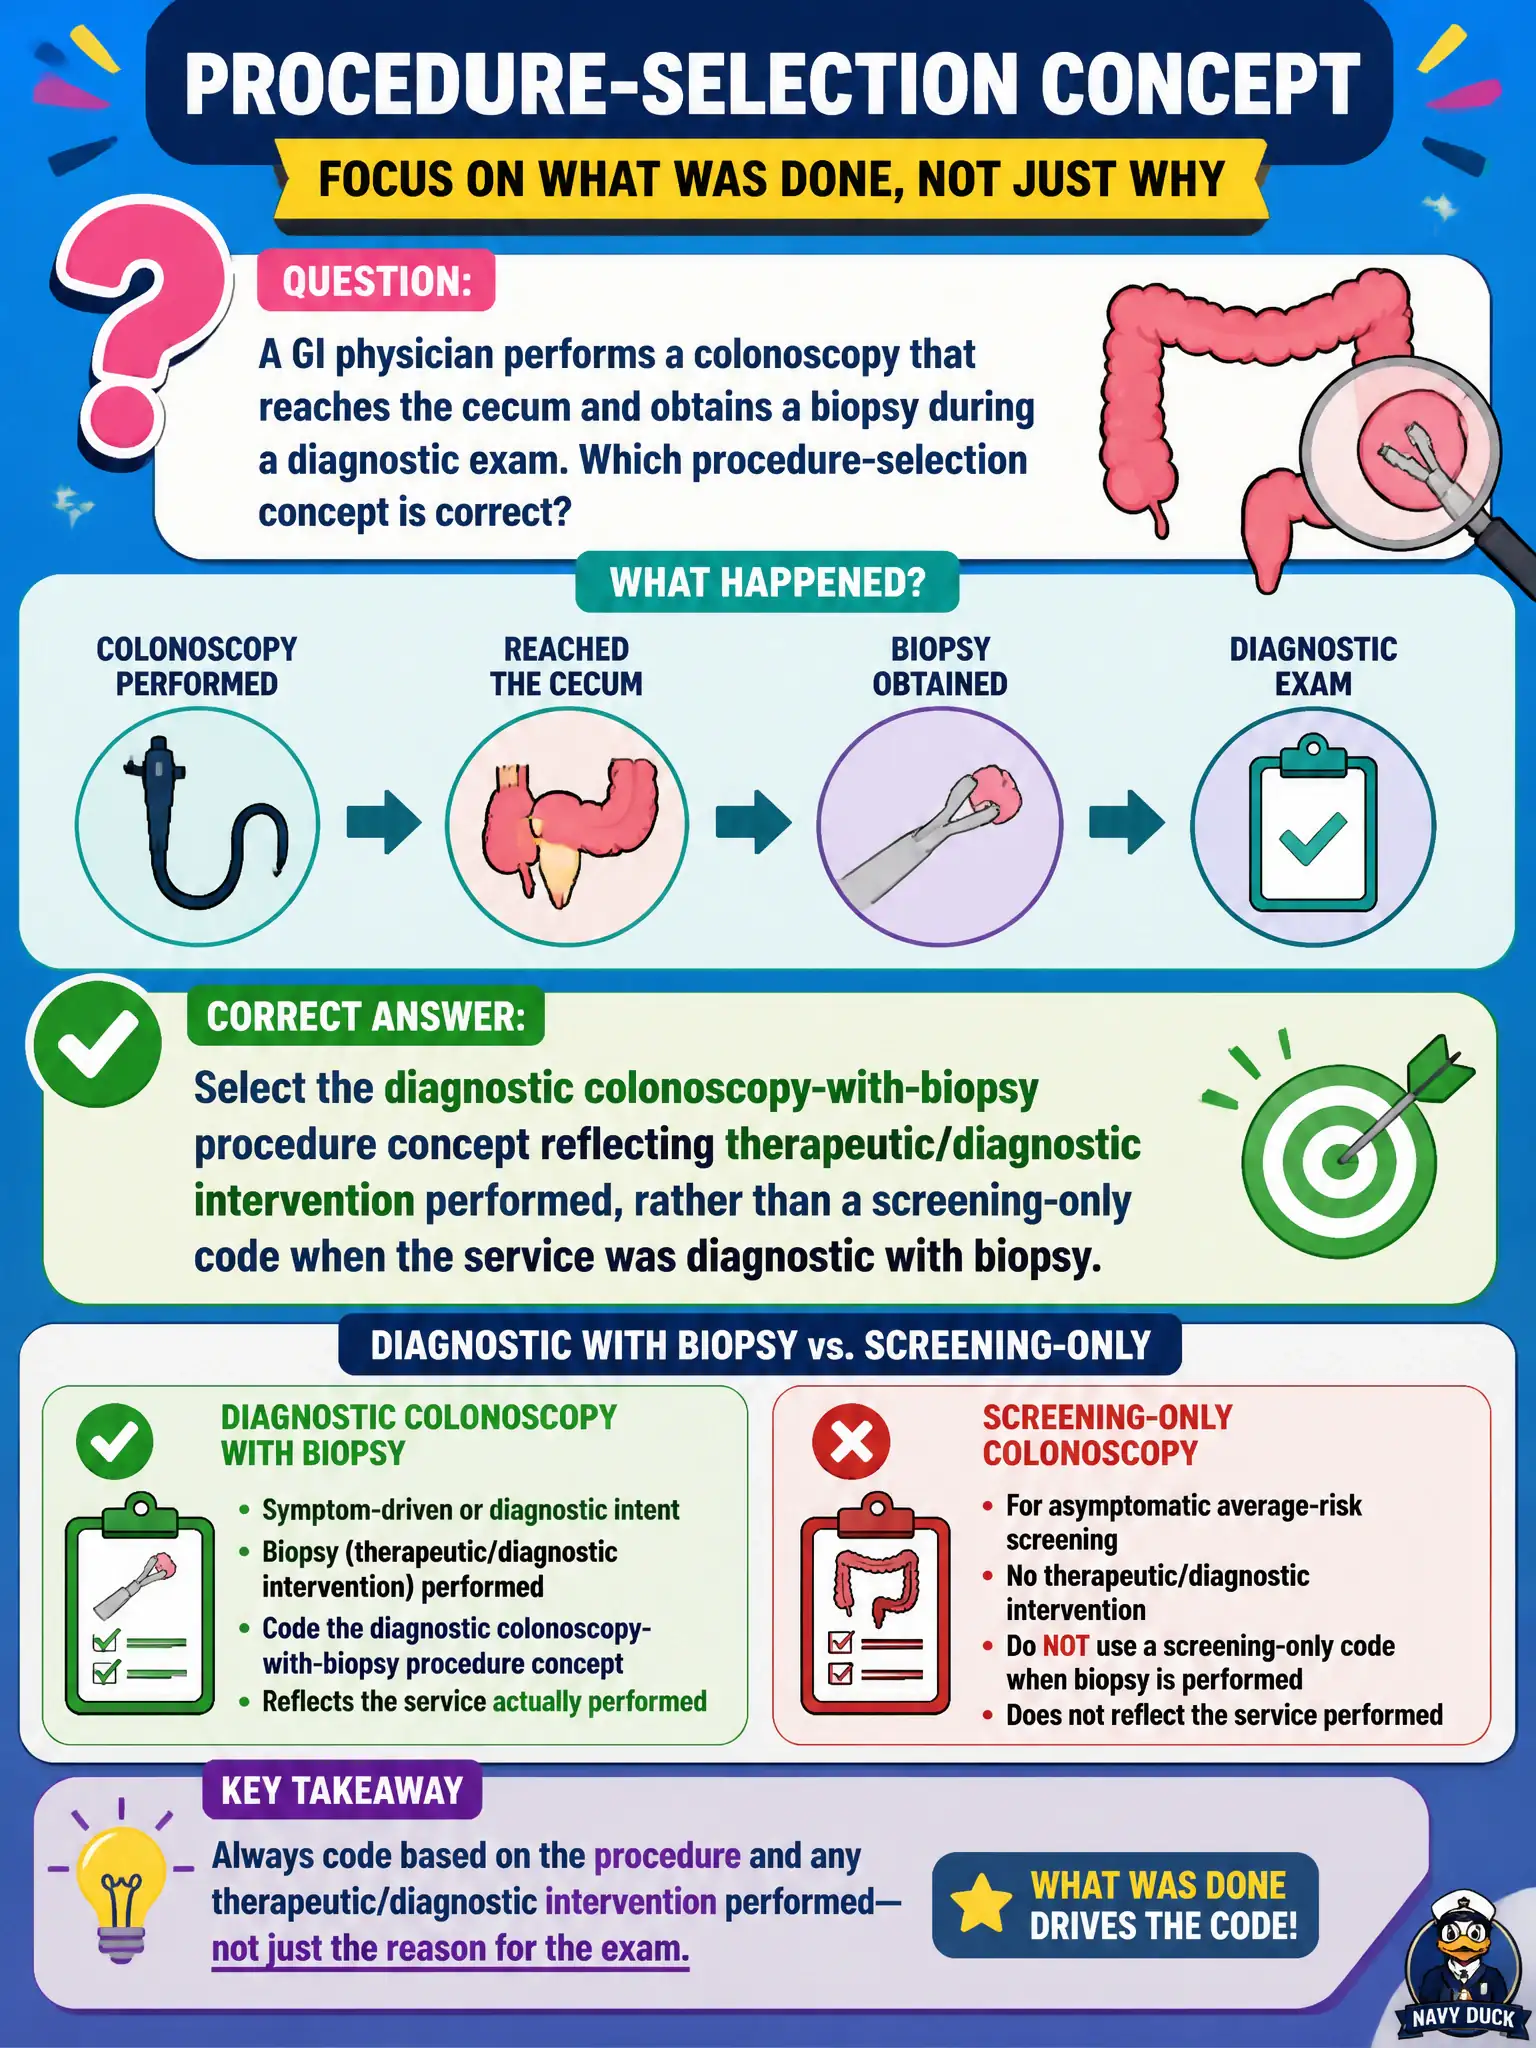
A GI physician performs a colonoscopy that reaches the cecum and obtains a biopsy during a diagnostic exam. Which procedure-selection concept is correct?
Select an answer to reveal the explanation.
Short Explanation
If you went in looking for trouble and took a snip, you’re not still waving the ‘screening flyer.’ Diagnostic colonoscopy with biopsy is its own lane. Screening-to-diagnostic conversion matters when a screen turns interventional—but here the note already describes a diagnostic exam with biopsy to the cecum.
Full Explanation
A diagnostic colonoscopy that reaches the cecum and includes biopsy is reported with the diagnostic colonoscopy-with-biopsy procedure concept reflecting the intervention performed, not a screening-only code when the encounter was diagnostic with biopsy. Accurate family selection in community GI practices prevents mislabeling therapeutic or diagnostic work as screening and preserves integrity of preventive-versus-diagnostic utilization reporting.
Always keeping a screening colonoscopy code even after biopsy if the patient is average risk ignores conversion and diagnostic-with-intervention concepts when the service performed is no longer a pure screen. Reporting only biopsy pathology codes and never a colonoscopy procedure erases the endoscopic service the physician performed. Coding an incomplete colonoscopy whenever any biopsy is taken, regardless of cecal intubation, invents incompleteness the note contradicts when the cecum was reached.
Exam caveat: screening-to-diagnostic conversion rules and payer coverage policies can still affect how the service is labeled for payment—apply the rule set for that claim year. Operational check: verify cecal intubation, biopsy documentation, and whether the exam began as screening or diagnostic, then select the colonoscopy family that matches the documented work.