
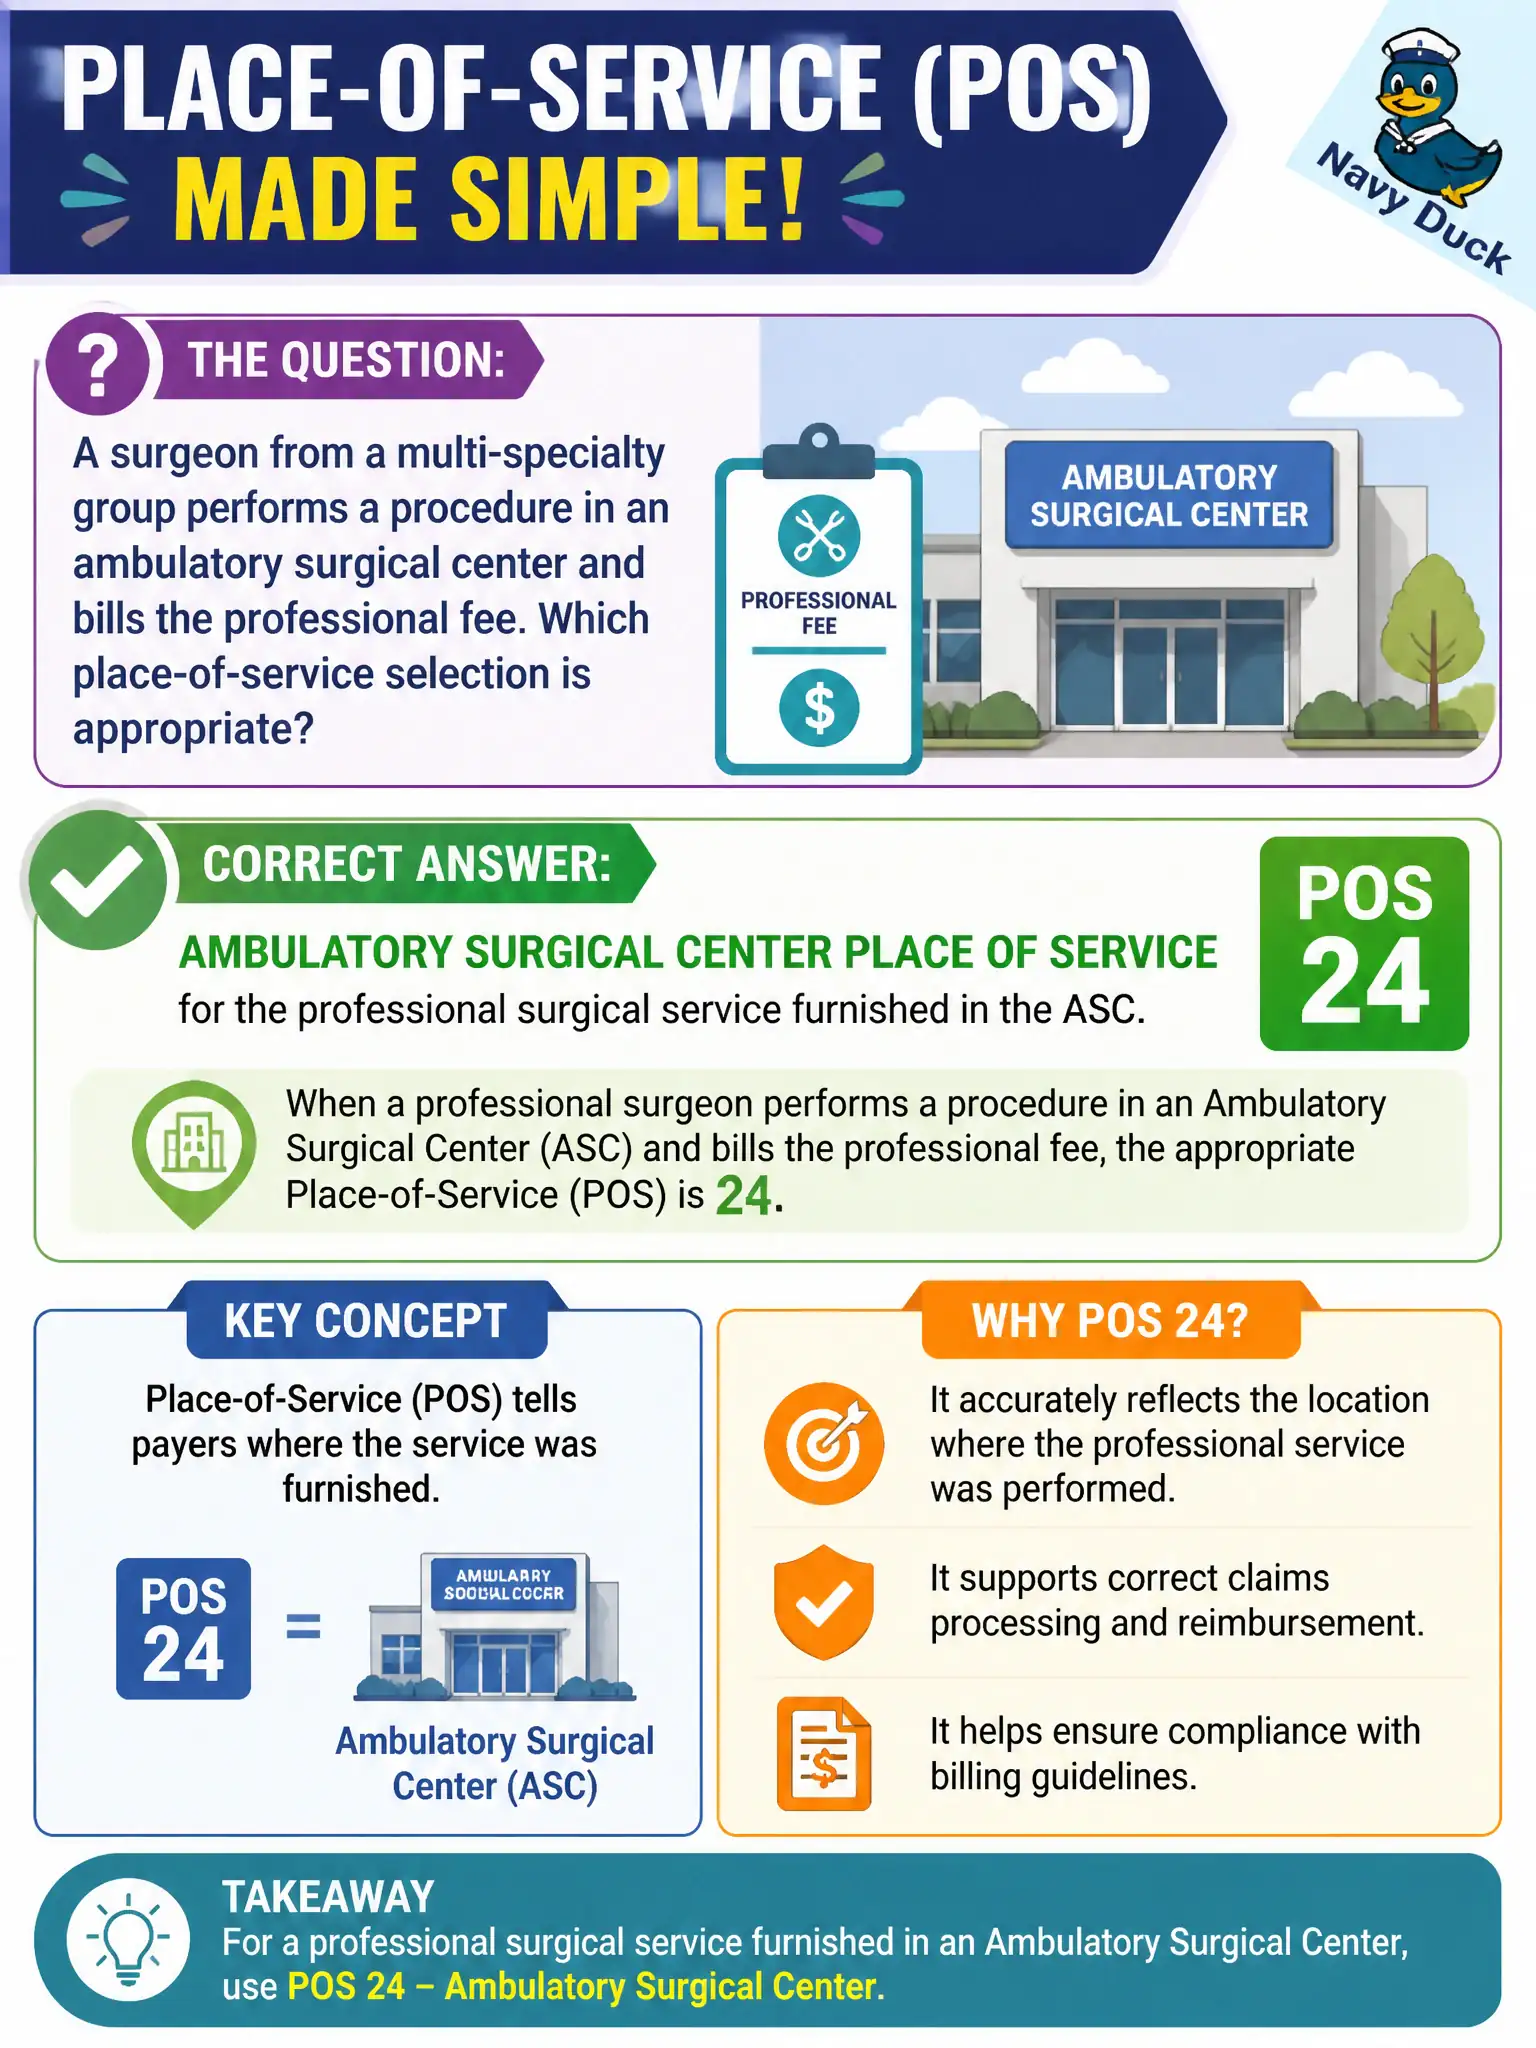
A surgeon from a multi-specialty group performs a procedure in an ambulatory surgical center and bills the professional fee. Which place-of-service selection is appropriate?
Select an answer to reveal the explanation.
Short Explanation
Surgery in an ASC gets ASC place of service on the professional claim—not last week’s office visit POS. Anesthesia doesn’t magically make it inpatient. Point POS at the ASC where the knife work happened.
Full Explanation
When a surgeon from a multi-specialty group performs a procedure in an ambulatory surgical center and bills the professional fee, the professional claim should carry ambulatory surgical center place of service. POS points to where the surgical service was furnished—the ASC—not to last week’s clinic clearance visit or to a generic “not office” hospital label. Correct ASC POS supports proper site-of-service payment for professional surgery claims tied to civic outpatient surgical centers.
Using office POS because preoperative clearance occurred in clinic last week fails by concept because a prior office encounter does not redefine the surgery’s location. Using inpatient hospital POS merely because anesthesia was administered fails because anesthesia does not equal inpatient status or inpatient POS. Using outpatient hospital POS for every non-office surgery fails because ASCs are not outpatient hospital departments and have their own POS construct.
Exam caveat: facility/ASC billing for the center is separate from the surgeon’s professional claim; both must reflect the ASC setting appropriately under their claim forms. Operational check: verify the operative location is listed as ASC in the OR schedule and operative note, assign ASC POS on the CMS-1500, and do not inherit POS from the preoperative office visit.