
A healthcare multi-agent system must block PHI leakage, unsafe tool use, and non-compliant model outputs. Architects want defense-in-depth rather than a single filter at the end of the chat. Which guardrail strategy best matches multi-intervention design for multi-agent solutions?
Select an answer to reveal the explanation.
Short Explanation
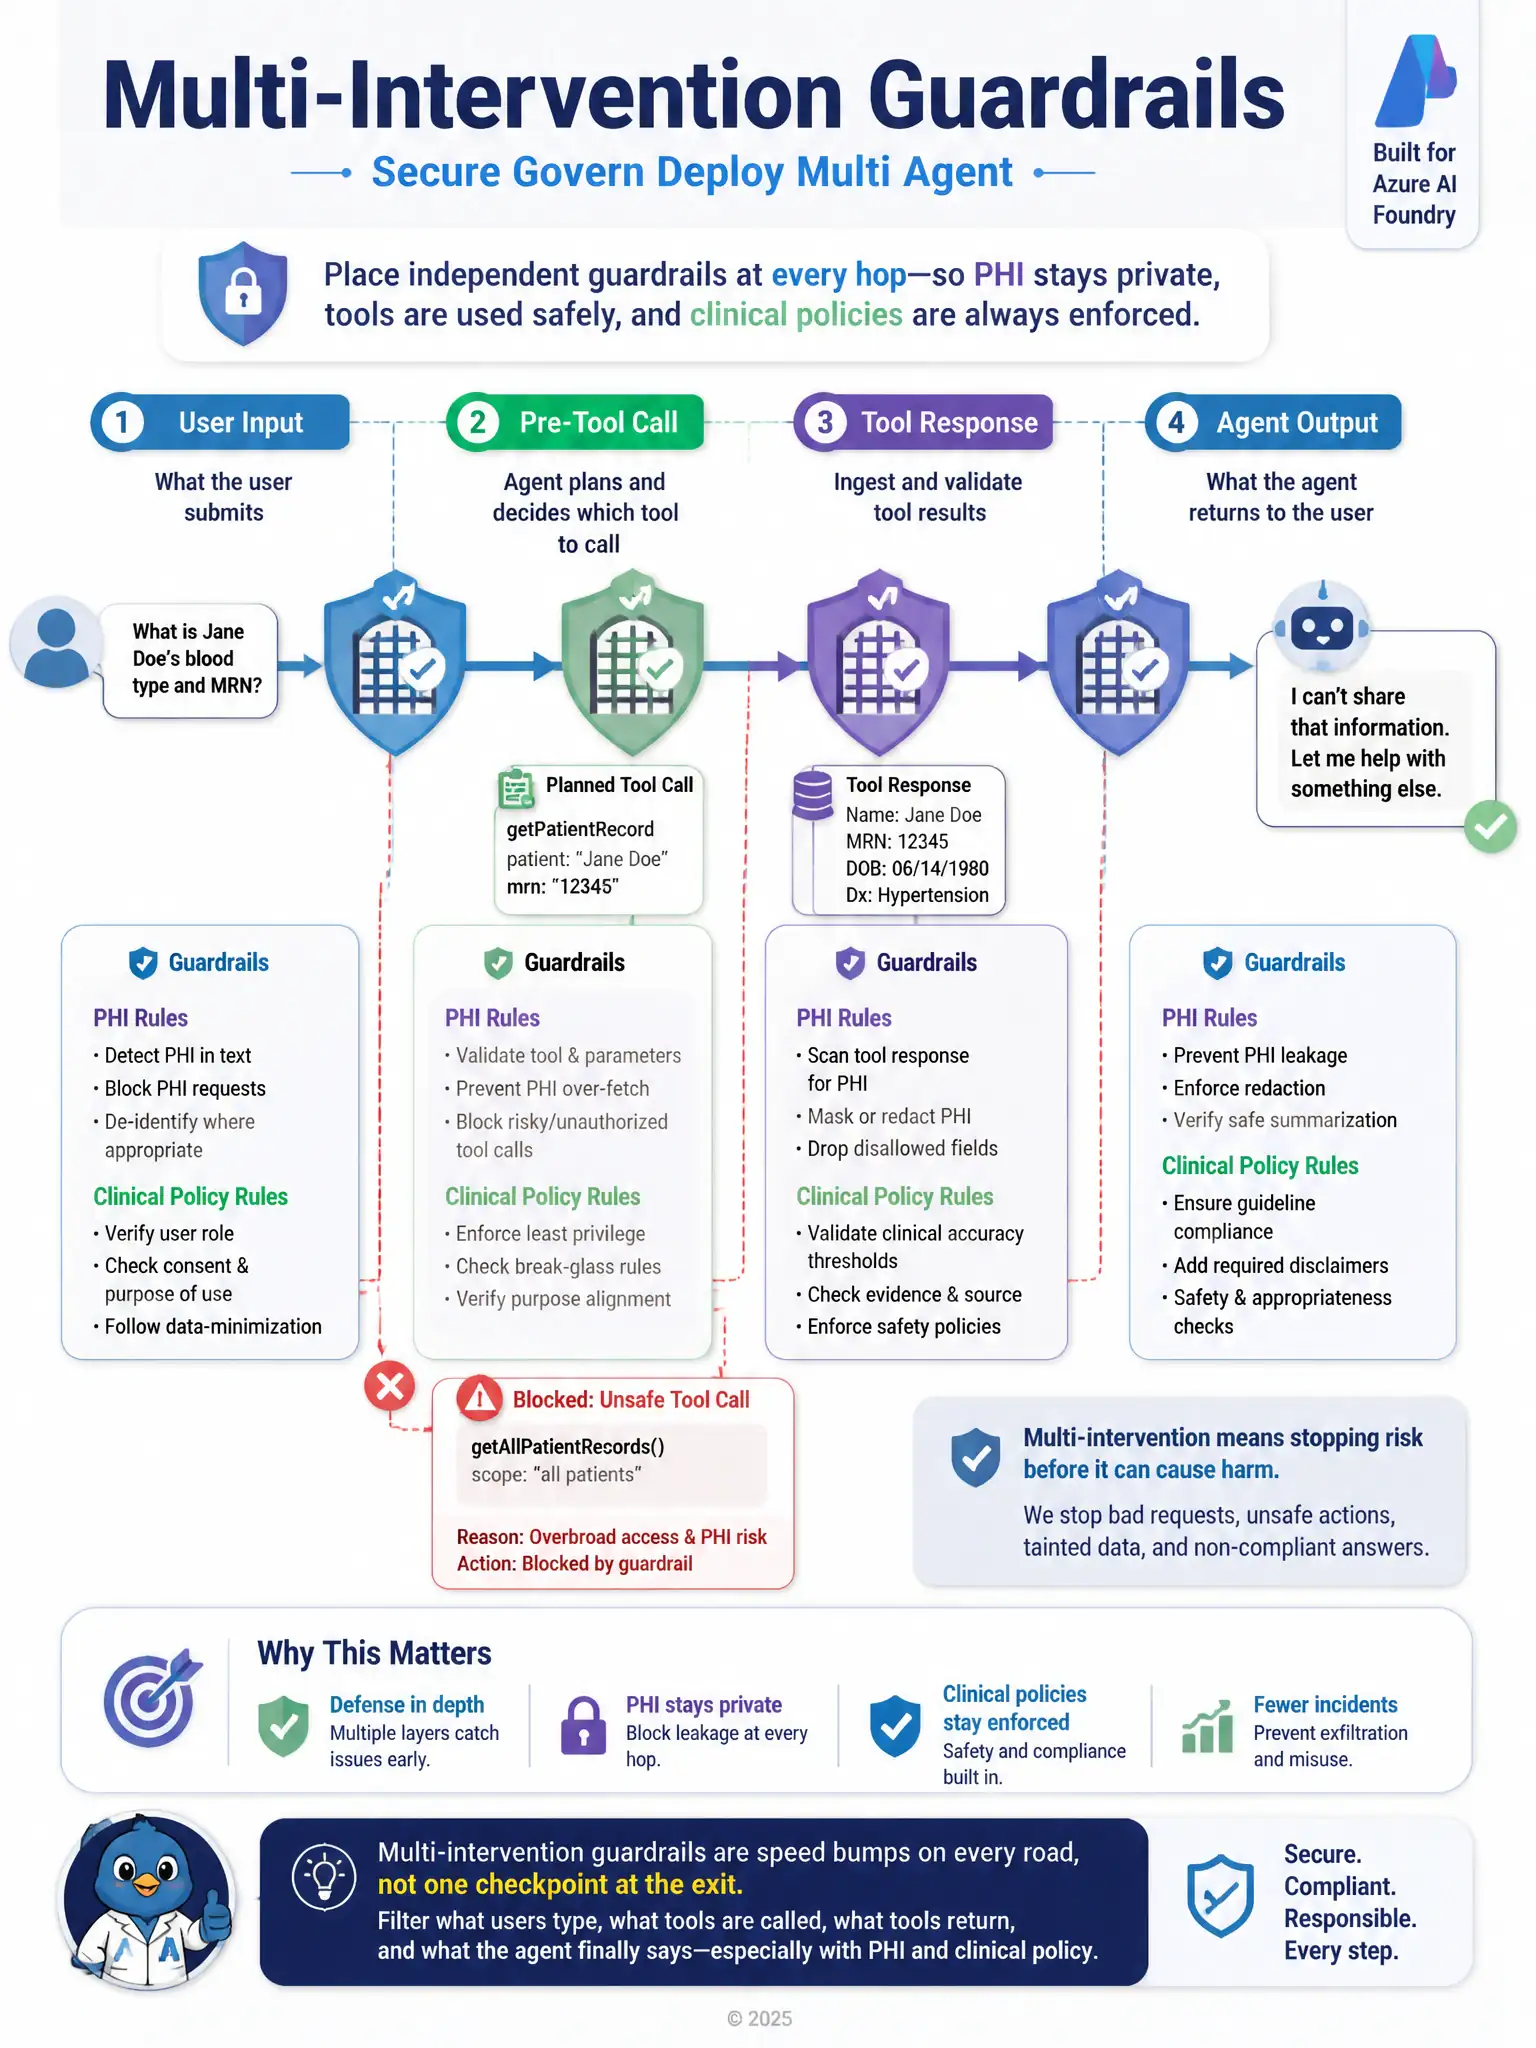
You need guardrails at every hop—input, tool planning, tool results, and output—so PHI or unsafe actions don't slip through. You don't want one checkpoint at the exit; filter what users type, what tools try to call, what tools return, and what the agent finally says.
Full Explanation
Microsoft’s multi-agent security guidance emphasizes multi-intervention guardrails: controls at user inputs, pre-tool-call planning, tool responses, and outputs. The staged guardrail approach is correct because it implements independent checks at each stage and layers domain-specific PHI and clinical constraints, so a jailbreak that slips past input filters can still be blocked before a dangerous tool call or before a PHI-laden tool result is echoed to the user.
The final-answer-only approach is incorrect because filtering only the final answer leaves intermediate tool invocations and tool responses unprotected—classic single-point-of-failure design.
The disable-tools approach is incorrect: removing tools may reduce attack surface but fails clinical workflows that need electronic health record or knowledge tools, and parametric-only answers increase hallucination risk for medical content.
The after-the-fact logging approach is incorrect because after-the-fact weekly review is detective, not preventive; it does not stop live leakage.
Exam tip: When the stem asks for multi-intervention or defense-in-depth guardrails, the correct answer enumerates input + tool-call + tool-response + output controls, often with custom domain rules.