
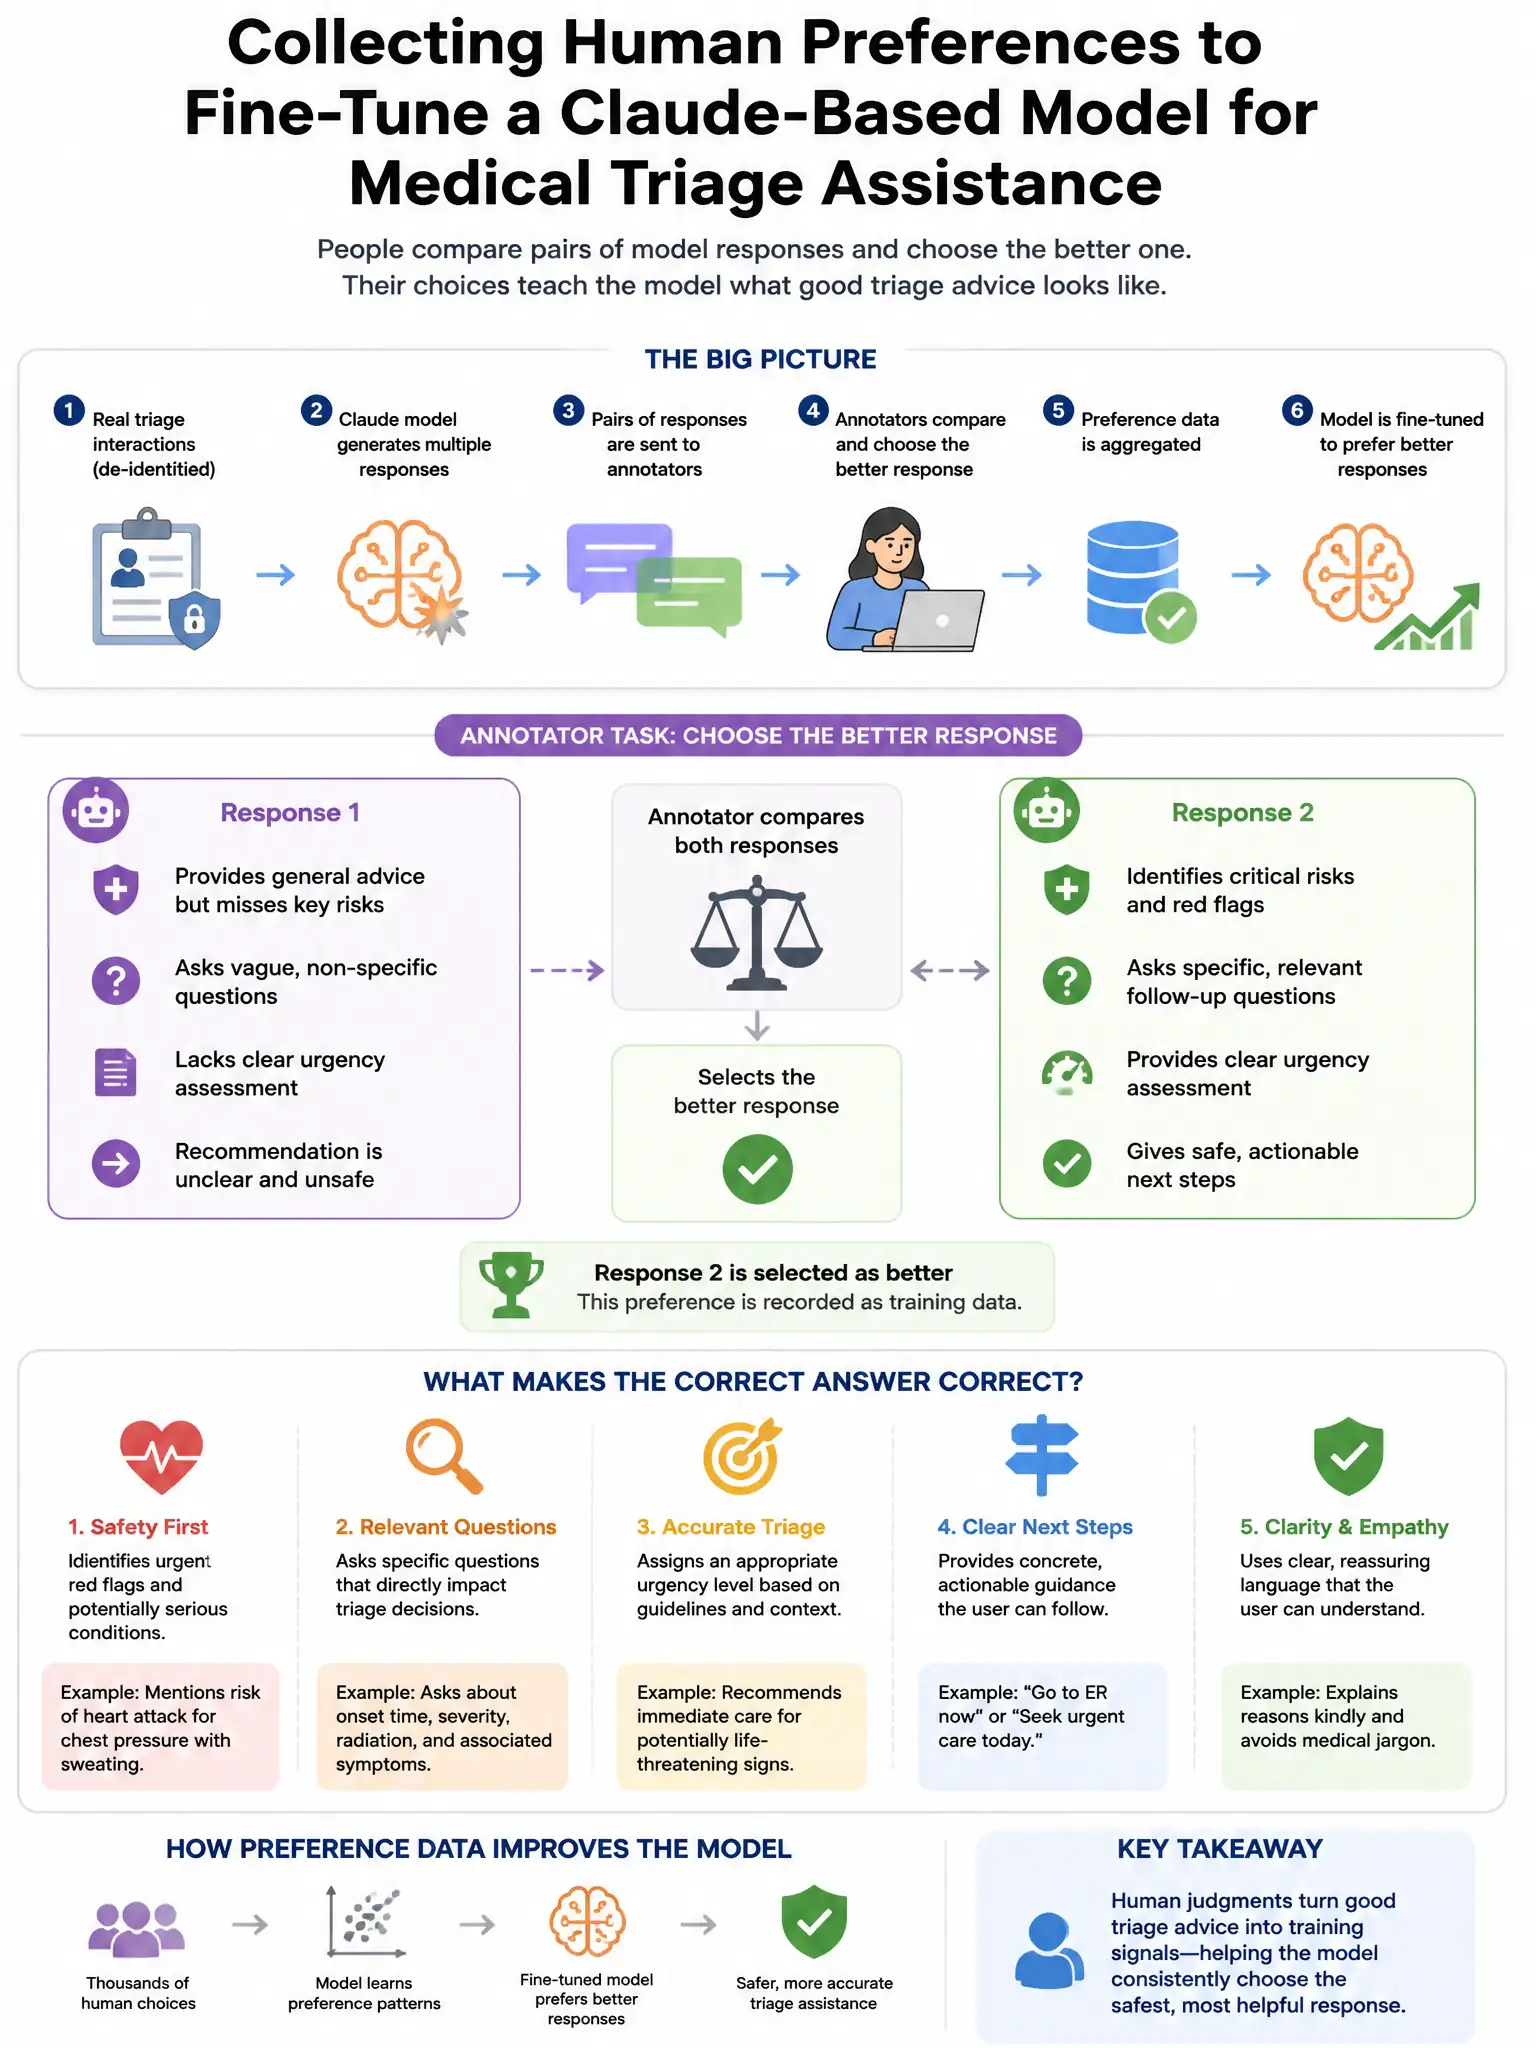
A team is collecting human preference data to fine-tune a Claude-based model for medical triage assistance. Annotators compare pairs of model responses and select the better one. A quality audit reveals that annotators frequently prefer responses that sound confident and authoritative even when the confident response contains a subtle medical error. What data collection design change addresses this quality problem?
Select an answer to reveal the explanation.
Short Explanation
Here's the deal — you need to stop annotators from rewarding confident-sounding answers over medically accurate ones. Require medical-background annotators, or use structured rubrics that force factual accuracy to be judged separately from stylistic confidence before a preference is marked.
Full Explanation
The design change that addresses the quality problem is requiring annotators to have medical backgrounds for all preference pairs, or providing structured evaluation rubrics that require explicit evaluation of factual accuracy separate from stylistic confidence before marking a preference. The problem is that annotators are conflating stylistic confidence with factual accuracy — a known bias in RLHF data collection. The fix is either domain expertise (medical annotators can evaluate accuracy) or structured rubrics that force explicit accuracy evaluation as a separate dimension before preference selection. Structured rubrics can work with general annotators by making accuracy evaluation a required step rather than an intuitive holistic judgment. Increasing the number of annotators per pair from 3 to 7 is wrong because it amplifies the bias — more annotators all sharing the confidence-preference bias produces a more confident but still inaccurate preference signal. Adding more diverse response pairs to the dataset to balance confident and uncertain responses is wrong because it does not address the annotation bias — annotators evaluating the new pairs still apply the same confidence-preference heuristic. Using a different annotation platform with better tooling is wrong because the problem is annotation methodology and evaluator expertise, not tooling — better software does not fix the accuracy vs. confidence confusion.